
ChondroFiller injection outcomes in 2026
How ChondroFiller injection works inside the joint
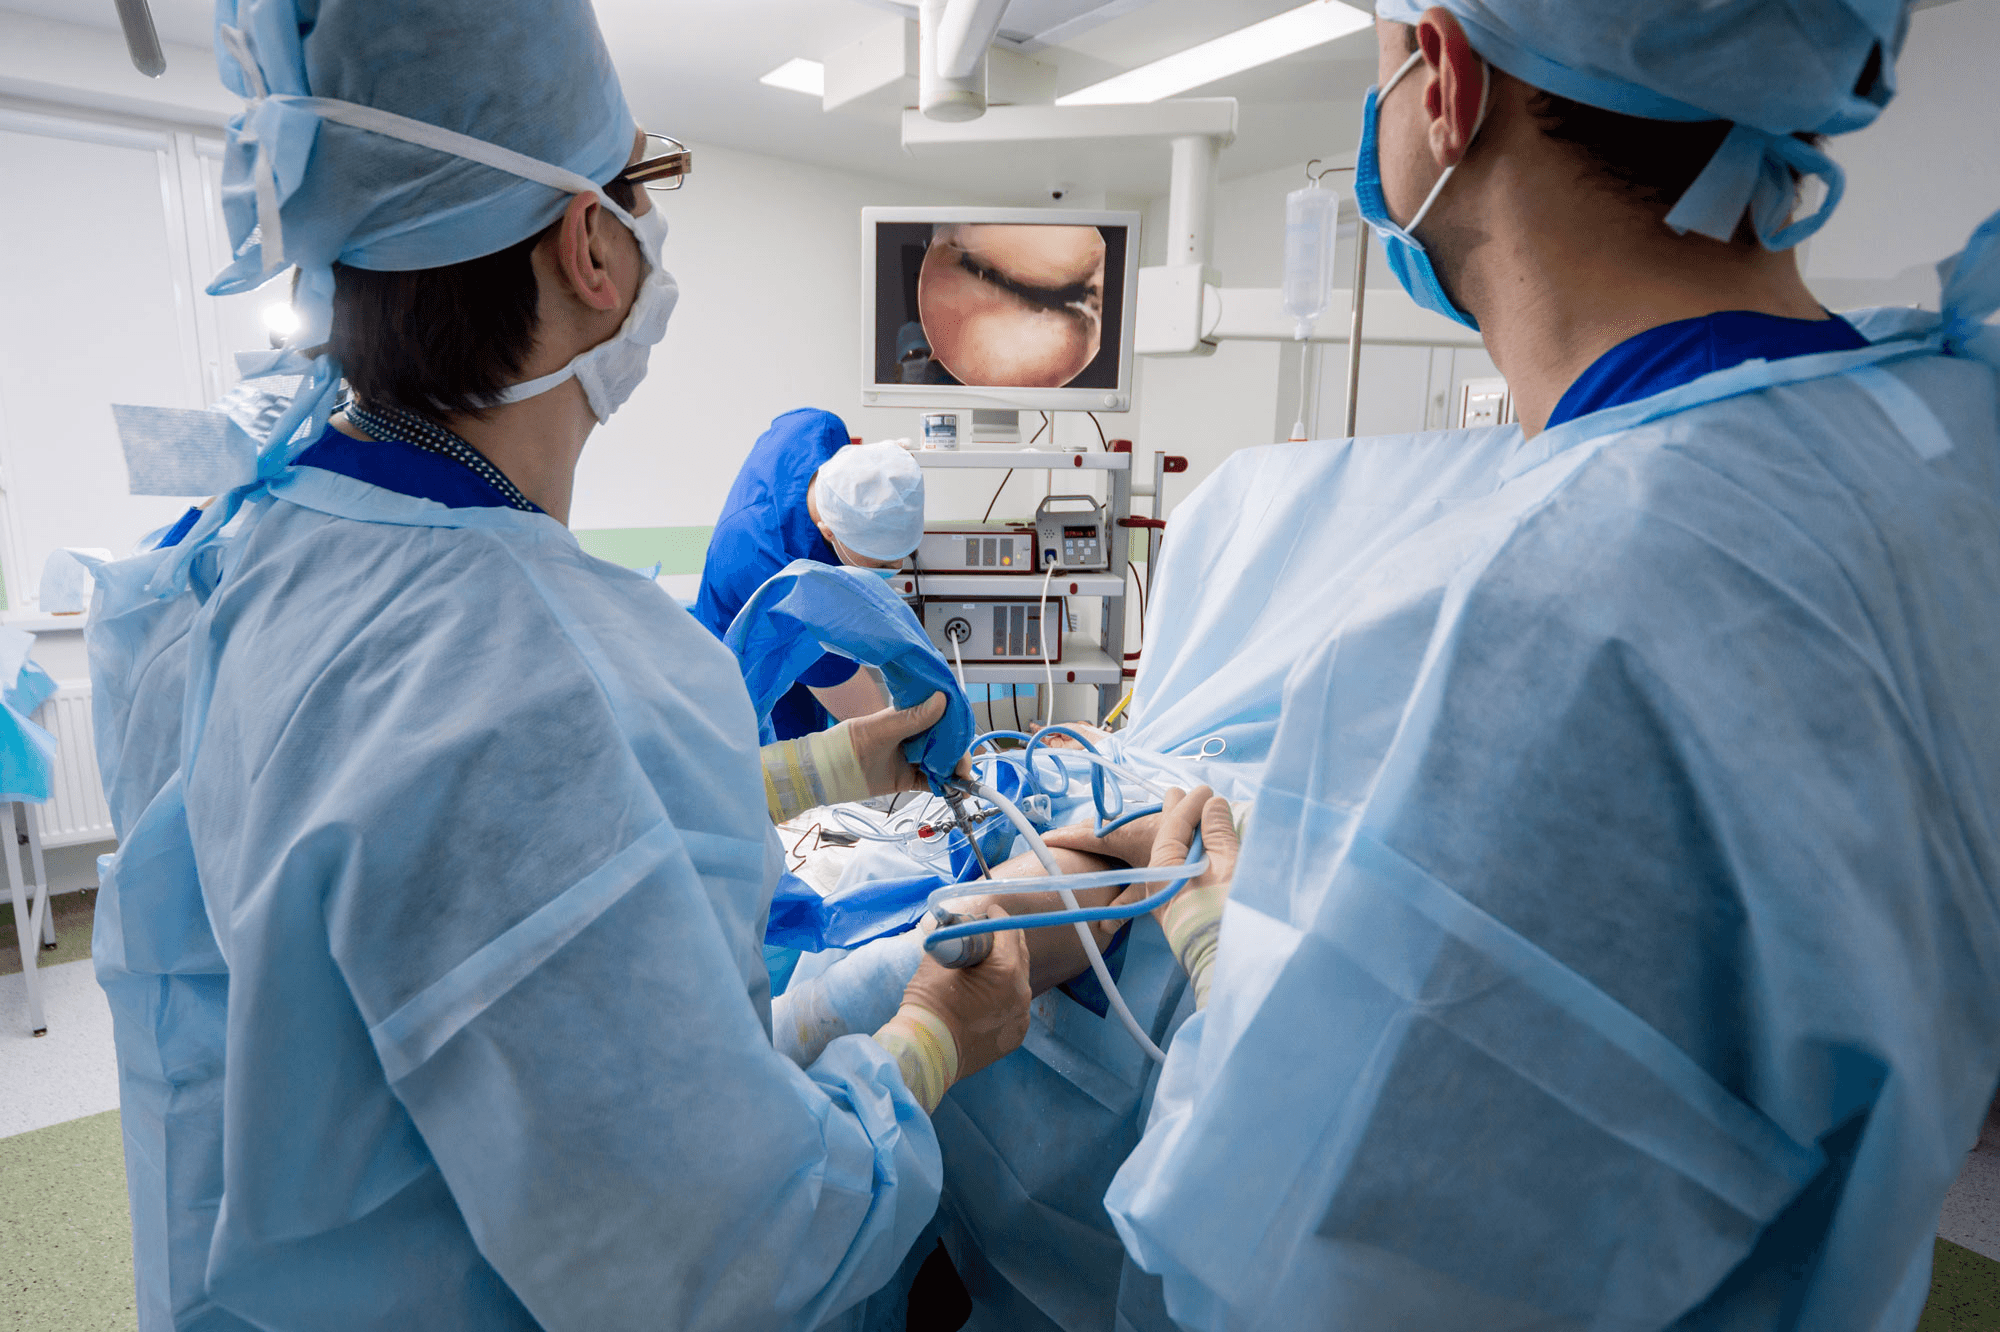
The moment ChondroFiller enters the joint, its chemistry takes over. Delivered as an ultrasound-guided outpatient injection at the London Cartilage Clinic on Harley Street, the material is a two-component collagen type I hydrogel — cell-free, so nothing from an external donor is introduced. As soon as the liquid components meet inside the joint space, they polymerise in situ, solidifying into a three-dimensional scaffold that conforms to the shape of the cartilage defect without any surgical preparation or theatre setting.
The scaffold's job is not to replace cartilage directly but to create the right environment for the body to repair it. This mechanism is called acellular matrix-induced chondrogenesis: the collagen matrix acts as a homing signal, drawing the patient's own progenitor cells — originating from the synovium and subchondral bone — into the defect site, where they begin laying down new matrix. The process supports the body's own repair process rather than introducing a finished tissue.
ChondroFiller is available in gel and liquid formulations; both follow the same core principle of in situ gelation and cell recruitment. The treating clinician selects the formulation based on the defect geometry and technique requirements — a decision made at assessment, not by the patient.
What the knee clinical trials show
Clinical trial data for the knee provide the strongest published evidence currently available for ChondroFiller, and the picture they paint is encouraging — with important caveats about trial size and design.
The most rigorous study to date is a 2016 prospective randomised multicenter trial comparing ChondroFiller liquid against microfracture in patients with focal knee cartilage defects. The ChondroFiller arm (n=13) recorded statistically significant IKDC score improvements at 3 and 6 months (p<0.05), maintained through to 12 months, with no adverse events reported across the cohort. MRI assessment at 4 and 52 weeks showed good immediate defect filling, confirmed integration with adjacent cartilage from an early stage, and progressive maturation of the reconstructed cartilage tissue by the one-year mark.
One structural limitation tempers the comparison: 6 of the 10 patients allocated to microfracture refused the allocated surgery and dropped out, leaving too small a comparator group for a formal head-to-head conclusion. The trial established feasibility and safety; it did not establish superiority over microfracture.
A 2024 knee series from University Hospital Pleven, Bulgaria (n=17, mean age 31 years, drawing on experience from 2012 to 2023) adds corroborating real-world data. Lysholm and IKDC scores improved significantly at 3, 6, and 12 months post-treatment (p<0.05), broadly consistent with an approximate 30-point IKDC gain seen across the published literature. Notably, the improvement plateau between the 6- and 12-month assessments was not statistically significant (p>0.05), suggesting that most of the functional recovery is established within the first six months — a useful reference point when setting expectations at the point of assessment.
Evidence across other joints: hip and wrist data
Hip and wrist data sit outside the knee trial literature but both contribute meaningful outcome signals for different joint sites.
The hip cohort — published in 2021 and covering 26 patients with acetabular cartilage lesions greater than 2 cm², followed for between 12 and 60 months — found that 17 of 21 evaluable patients achieved good or excellent long-term results, with modified Harris Hip Score gains in the region of 30 points reflecting clinically significant functional improvement. Two patients in the cohort eventually required total hip replacement. A clear selection signal emerged alongside those results: patients with pre-existing moderate-to-severe osteoarthritis (Tönnis grade 2–3) consistently recorded poor outcomes, a pattern that holds relevance across joint sites when considering suitability. This cohort used arthroscopic surgical delivery and is best understood as background evidence supporting the biological mechanism rather than a description of the current outpatient injection pathway.
The most recent peer-reviewed data come from a 2025 prospective study of 59 intra-articular distal radius fractures, with 25 patients receiving ChondroFiller. Follow-up arthroscopy found significantly better cartilage quality in the treated group: median Outerbridge score 1.5 versus 3 in matched controls (P=0.006) and ICRS grade 1 versus 3 (P=0.002). On technique, the study identified overfilling as the sole driver of fibrous tissue formation — flush application produced none of it. That precision requirement is not unique to the wrist: the volume and placement of the material are outcome variables in their own right, regardless of the joint being treated.
What lab and biomechanics research adds to the picture
Laboratory studies cannot tell us how a patient will feel after treatment, but they can explain why a recovery protocol is structured the way it is — and where future combination strategies may carry added value.
A 2025 ex vivo osteochondral biomimetic model found that ChondroFiller® alone produced a 2.4-fold increase in DNA content within defect tissue by day 14, indicating active cell recruitment into the scaffold even without any added cells. When mesenchymal stem cells (MSCs) were introduced alongside it, collagen deposition and glycosaminoglycan (GAG) production increased further. This points toward an additive effect from cell-based combination strategies — a clinically relevant signal, though it comes from a laboratory model rather than a clinical trial and should be understood accordingly. At assessment, it is worth raising whether a combination approach involving biologics such as autologous MSCs may be appropriate for your particular defect.
A separate 2024 biomechanical in vitro study raised a practical caution: under cyclic loading of 33 N applied early, ChondroFiller could not protect the opposing cartilage surface, attributed to initial scaffold instability before the material has fully integrated. The authors concluded that joint loading should be delayed until stable defect filling is achieved. This finding directly supports the protected weight-bearing period that follows injection — early activity restriction is not precautionary excess; it allows the scaffold time to consolidate.
Together, these two studies reinforce two patient-facing principles: rest the joint early, and consider whether a biologic partner alongside the ChondroFiller scaffold is worth discussing at the consultation stage.
Where the evidence still has limits
The evidence base for ChondroFiller is growing, but several limits deserve plain acknowledgement before a patient or clinician draws conclusions from the published literature.
Every clinical study conducted to date has enrolled fewer than 30 patients. No adequately powered randomised controlled trial with an active comparator and complete follow-up has been published. The 2016 knee RCT remains the most rigorous design available, and even that study's comparator arm was incomplete — 6 of 10 microfracture patients refused the allocated procedure, preventing any formal superiority conclusion. The 2024 knee series and 2025 wrist data are meaningful additions to the literature, but neither was designed to compare ChondroFiller against an alternative treatment.
Long-term outcomes are also an open question. The hip cohort followed patients for up to 60 months, but nothing in the peer-reviewed literature extends the picture systematically beyond five years. Whether functional gains are sustained at decade-level follow-up, and under what conditions, is not yet known.
The most significant gap for patients considering the current outpatient injection pathway is that no published RCT has evaluated ChondroFiller delivered by non-surgical injection. The clinical trial data — including the 2016 randomised study and the hip and wrist series — were generated through arthroscopic or surgical implantation. The outpatient injection route is supported by the mechanistic rationale and the adjacent surgical evidence, but it has not been tested directly in a controlled trial. That gap is real and is a legitimate factor in any informed decision.
The broader field shares similar constraints. A 2025 systematic review of adjuvant injection therapies following bone marrow stimulation for knee cartilage defects found heterogeneous evidence across all modalities, with no single agent demonstrating consistent superiority. ChondroFiller sits within a field that is still accumulating the controlled data needed to answer comparative questions with confidence.
Who is most likely to benefit and what assessment involves
Patient selection is where the published outcomes diverge most clearly. The evidence consistently favours younger patients with focal, contained cartilage defects and no significant underlying osteoarthritis — the hip cohort established that Tönnis grade 2–3 disease reliably predicts poor outcomes, a principle that applies across joint sites. The 2024 knee series, drawn from patients with a mean age of 31 years, reflects a similar profile: active adults with discrete defects rather than diffuse joint-surface degeneration.
For patients with more widespread, early-to-mid OA, a ChondroFiller injection may still be appropriate — in that context, the scaffold functions as a mechanical cushion over worn articular surface rather than repairing a single focal defect. This is a materially different indication, and whether it is suitable depends on individual clinical and imaging findings that cannot be determined without a structured assessment.
At London Cartilage Clinic on Harley Street, that assessment includes MRI or ultrasound imaging review to characterise defect depth, size, and the condition of surrounding cartilage; grading of OA severity to establish whether the patient falls within a range where ChondroFiller injection is likely to add value; and evaluation of clinical history — loading demands, prior interventions, and symptom trajectory — that together shape treatment planning. The 2025 wrist data showed that placement precision is itself an outcome determinant; Professor Paul Y. F. Lee, who leads Liquid Cartilage™ delivery at the clinic, brings that technique focus to every case.
To arrange an assessment, visit londoncartilage.com.
- [1] Arthroscopic utilization of ChondroFiller gel for the treatment of hip articular cartilage defects: a cohort study with 12- to 60-month follow-up. (2021). https://doi.org/10.1093/jhps/hnab002 https://doi.org/10.1093/jhps/hnab002
- [2] IMPLANTATION OF CHONDROFILLER LIQUID® AS A SCAFFOLD MATERIAL FOR THE TREATMENT OF CHONDRAL LESIONS OF THE KNEE JOINT. (2024). https://doi.org/10.5272/jimab.2024304.5936 https://doi.org/10.5272/jimab.2024304.5936
- [3] Controlled, randomized multicenter study to compare compatibility and safety of ChondroFiller liquid with microfracturing of patients with focal cartilage defects of the knee joint. (2016). https://doi.org/10.5348/VNP05-2016-1-OA-1 https://doi.org/10.5348/VNP05-2016-1-OA-1
- [4] Cartilage reconstruction using Chondrofiller in intra-articular distal radius fractures. (2025). https://doi.org/10.1186/s42836-025-00333-y https://doi.org/10.1186/s42836-025-00333-y
- [5] Influence of cartilage defects and a collagen gel on integrity of corresponding intact cartilage: a biomechanical in-vitro study. (2024). https://doi.org/10.1007/s00402-024-05530-z https://doi.org/10.1007/s00402-024-05530-z
- [6] Development of an Ex Vivo Osteochondral Biomimetic Platform for Mechanistic Investigation of Cartilage Regeneration. (2025). https://doi.org/10.3390/ijms262311759 https://doi.org/10.3390/ijms262311759
- [7] Adjuvant injection therapies following knee cartilage repair demonstrate heterogeneous evidence: A systematic review. (2025). https://doi.org/10.1002/jeo2.70555 https://doi.org/10.1002/jeo2.70555
Frequently Asked Questions
- ChondroFiller is a two-component collagen type I hydrogel delivered as an ultrasound-guided injection. Upon entering the joint, its liquid components polymerise in situ, forming a three-dimensional scaffold that conforms to the cartilage defect without requiring surgery.
- ChondroFiller draws the patient's own progenitor cells into the defect, where they lay down new matrix. The scaffold supports the body's repair process rather than directly replacing cartilage.
- The 2016 knee trial (n=13) showed statistically significant IKDC improvements at 3 and 6 months, maintained at 12 months. A 2024 series (n=17) found similar results, with most recovery within six months.
- Younger patients with focal, contained cartilage defects and no significant underlying osteoarthritis are most likely to benefit. Evidence favours active adults with discrete defects rather than diffuse joint-surface degeneration.
- Assessment includes MRI or ultrasound imaging to characterise defect depth and size, grading of osteoarthritis severity, and evaluation of clinical history including loading demands and prior interventions.
Next steps
Where to go from here
These routes are selected from the topic and purpose of this article. They are guidance, not a diagnosis or treatment recommendation.
Learn more
Explore ChondroFiller
Read the reviewed ChondroFiller pathway, including who it may help and what happens next.
Self-assessment
Try the ChondroFiller suitability check
Answer a short set of questions for a useful, non-diagnostic next-step guide.
Talk to the team
Book a free discovery call
A non-medical call with the team to understand services and choose the right booking route.
Legal & Medical Disclaimer
This article is written by an independent contributor and reflects their own views and experience, not necessarily those of Liquid Cartilage. It is provided for general information and education only and does not constitute medical advice, diagnosis, or treatment.
Always seek personalised advice from a qualified healthcare professional before making decisions about your health. Liquid Cartilage accepts no responsibility for errors, omissions, third-party content, or any loss, damage, or injury arising from reliance on this material.
If you believe this article contains inaccurate or infringing content, please contact us at [email protected].