
ChondroFiller Injection for Elbow Cartilage Damage
Which elbow cartilage injuries are suitable?
Whether a specific elbow injury qualifies for ChondroFiller injection comes down to two filters: defect depth and containment.
The treatment is designed for focal Outerbridge or ICRS Grade III–IV cartilage lesions — damage that has reached the deepest layers of the cartilage surface, producing a discrete crater rather than a general thinning across the joint. The defect must be contained within a viable ring of surrounding cartilage, with a surface area no greater than 6 cm² (roughly 2.5 cm across). That intact border is not incidental — it is what holds the injected collagen scaffold in place while it sets and begins recruiting the body's own repair cells.
The three presentations that most commonly meet these criteria in the elbow are osteochondritis dissecans (OCD) of the capitellum, chondral shear injuries, and focal cartilage loss associated with lateral ligament disruption. OCD of the capitellum is the primary target diagnosis: 97% of elbow OCD lesions are capitellar, and the condition is particularly common in adolescent overhead-throwing athletes — baseball and cricket players — as well as gymnasts and tumblers whose elbows absorb repetitive compressive load.
Two presentations fall outside the indicated range. Bare-bone Grade IV lesions with no surrounding cartilage border cannot contain the scaffold, and diffuse elbow osteoarthritis — where damage is widespread rather than focal — is not an appropriate indication.
MRI is the key assessment tool. Lesion dimensions measured on MRI correlate strongly with intraoperative findings (r=0.81), making it the most reliable way to confirm defect size and assess whether the surrounding cartilage border is intact enough to proceed.
What the outpatient injection involves
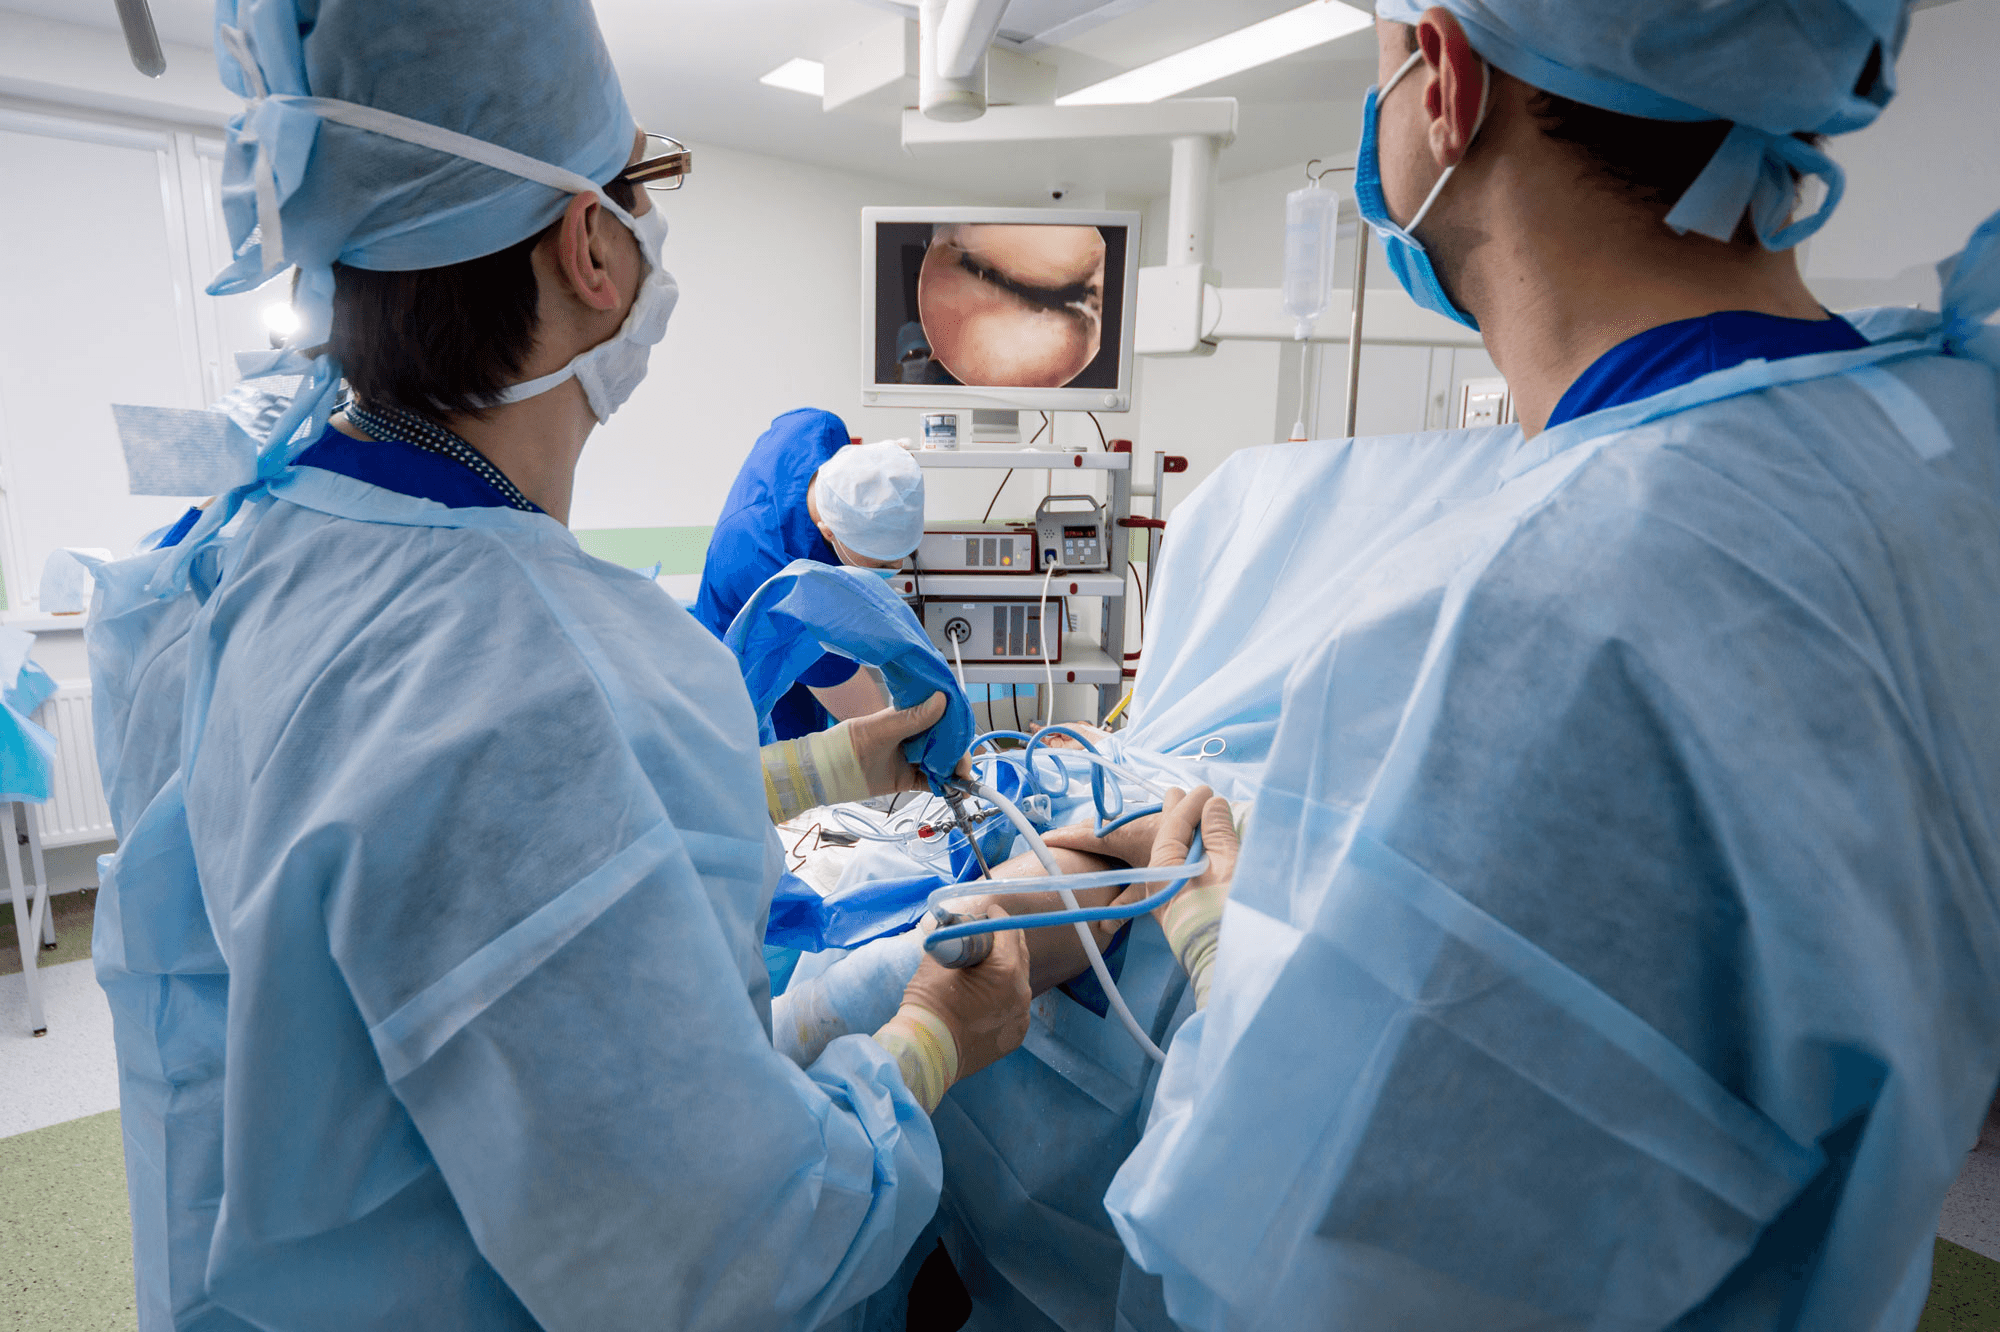
The appointment takes place at the London Cartilage Clinic on Harley Street as a straightforward outpatient visit — no general anaesthesia, no surgical incision, and no overnight admission. From arrival to discharge, the procedure typically takes 30 to 45 minutes.
Throughout the injection, the clinician uses real-time ultrasound to guide the needle to the precise site of the cartilage defect. In deep or anatomically complex joints, landmark-based injections miss the target in 28–30% of cases; ultrasound-guided placement achieves 100% accuracy. For a joint as compact as the elbow — where depositing the scaffold even a few millimetres wide of the lesion would waste the treatment — this level of imaging precision is directly relevant to the outcome.
Once the needle is correctly positioned, the liquid collagen is injected into the defect cavity, where it gels in situ within approximately three to five minutes, conforming to the contours of the lesion rather than sitting as a free liquid in the joint space.
How the scaffold is applied also affects the quality of tissue that forms. Biomechanical studies have confirmed that overfilling the defect — leaving the scaffold proud of the surrounding cartilage surface — leads to fibrous rather than cartilage-like tissue. The treating clinician therefore fills the defect flush to the native cartilage border, a step that requires both the right imaging and familiarity with the product's handling behaviour.
After the injection, elbow loading is deliberately restricted while the scaffold integrates. The scaffold has a period of initial mechanical vulnerability before it becomes stable, and the specific restriction period is set by the treating clinician according to the size and location of the defect.
How the scaffold recruits the body's own cells
Unlike cell-based cartilage repair procedures, ChondroFiller injection introduces no donor cells into the joint. The collagen scaffold itself — once it has gelled in the defect, as described above — does the signalling work: its three-dimensional matrix structure acts as a chemotactic environment, drawing the patient's own progenitor cells down into the lesion from the surrounding tissue and synovial fluid.
Once those cells have migrated into the scaffold, they begin to differentiate and produce cartilage-like matrix. This process is called matrix-induced chondrogenesis, and it is what distinguishes the treatment from a simple filler or cushioning agent — the aim is new tissue formation, not mechanical padding.
The scale of cell recruitment has been measured directly. In an ex vivo osteochondral model, ChondroFiller-treated defects showed a 2.4-fold increase in DNA content by day 14, confirming that the scaffold draws in a substantial cell population within the first two weeks. As that tissue matures over subsequent months, the collagen scaffold itself gradually resorbs, leaving behind repair tissue rather than a permanent foreign implant.
ChondroFiller is a CE-marked Class III medical device manufactured by Meidrix Biomedicals GmbH, with approximately two decades of European clinical use. It has been applied across multiple joints — including the knee, hip, shoulder, wrist, and small hand joints — as well as the elbow, giving the scaffold a broad track record even where elbow-specific published data remain limited.
What the clinical evidence shows for comparable joints
No published clinical trial has examined ChondroFiller injection specifically in the elbow. That absence is the most important context for the outcome data presented below: the clinical case for the treatment rests on adjacent-joint evidence and specialist extrapolation, not an elbow-specific trial programme.
The strongest functional data come from the knee. In a randomised controlled study, patients reported statistically significant IKDC and Lysholm score improvements at 3, 6, and 12 months, with a mean IKDC gain of approximately 32 points reported across ChondroFiller knee studies. Serial MRI (MOCART scoring) showed good immediate defect filling and progressive cartilage maturation through to 52 weeks, with no adverse events recorded.
Medium-term hip outcomes are also relevant to understanding durability. In a cohort of 26 patients with acetabular lesions greater than 2 cm², 17 of the 21 evaluable patients achieved good or excellent results at three to five years. The subgroup who had entered the study with pre-existing Tönnis Grade 2–3 osteoarthritis fared poorly — a finding that reinforces why diffuse joint disease is an exclusion criterion rather than an indication.
The wrist data are particularly instructive given the anatomical comparison: like the elbow, the wrist is a small, mechanically loaded joint with complex geometry. In a prospective cohort of 25 patients treated after intra-articular distal radius fractures, follow-up arthroscopy showed significantly better cartilage quality in the ChondroFiller group — median Outerbridge grade 1.5 versus 3 in controls (p=0.006), and ICRS grade 1 versus 3 (p=0.002).
Current guidance on ChondroFiller injection for elbow cartilage damage draws on expert clinical opinion from UK specialist centres, including the London Cartilage Clinic, rather than on independently confirmed elbow trial data. Patients should discuss realistic expectations during their assessment, with that distinction clearly in view.
ChondroFiller injection versus elbow surgery
Standard arthroscopic management of elbow OCD — typically debridement combined with microfracture — carries an 11% pooled revision rate across 20 published studies and 477 elbows, all classified as level IV evidence. Beyond the revision figure, the tissue microfracture produces is fibrocartilage rather than hyaline-like repair tissue: biomechanically inferior to native articular cartilage and prone to degradation over time. The procedure also disrupts the subchondral bone plate, which can narrow the options available if further intervention is later needed.
ChondroFiller injection takes a different route. As an ultrasound-guided outpatient procedure, it requires no theatre, no incision, and does not disturb the subchondral bone. Rather than triggering a marrow-stimulation healing response, the injectable scaffold targets matrix-induced chondrogenesis — recruiting the patient's own progenitor cells to form cartilage-like repair tissue within the defect.
It is fair to note that the surgical field is also developing scaffold-augmented approaches for elbow OCD, including techniques combining HYALOFAST with bone graft, extracellular matrix plus bone marrow aspirate concentrate, and BioCartilage-enhanced microfracture. Early results are encouraging, though the evidence remains preliminary and each approach still requires an operating theatre.
The two pathways are not always mutually exclusive. Patients who have previously undergone surgery and retain residual or recurrent cartilage damage may still be assessed for ChondroFiller injection — provided specialist review of post-operative imaging confirms that a contained, focal defect meeting the scaffold candidacy criteria remains present. That assessment is what determines whether injection remains a viable option.
Recovery, loading, and booking an assessment
Recovery after ChondroFiller injection for the elbow is graduated rather than immediate. Activity restrictions during the integration period are set by the treating clinician based on defect location and size — light daily use of the arm typically resumes before full mechanical loading of the joint is cleared. Progress is tracked through a structured follow-up programme; in knee cohorts, MRI at 52 weeks has been used to assess cartilage maturation and defect fill, and a comparable imaging checkpoint applies to other joints, including the elbow.
Patients who have already undergone elbow surgery and are wondering whether a ChondroFiller injection is still an option are also welcome to seek assessment — the key question is whether post-operative imaging confirms that a contained focal defect within the treatable range remains present. That imaging review, combined with a physical examination, is where individual suitability is established.
ChondroFiller injection for elbow cartilage damage is available at the London Cartilage Clinic on Harley Street, the UK's certified delivery centre for the treatment. The first step is a specialist assessment with MRI review; appointments can be booked at londoncartilage.com.
- [1] Implantation of ChondroFiller Liquid as scaffold for chondral lesions of the knee. (2024). https://doi.org/10.5272/jimab.2024304.5936 https://doi.org/10.5272/jimab.2024304.5936
- [2] Ex vivo osteochondral biomimetic platform for cartilage regeneration investigation. (2025). https://doi.org/10.3390/ijms262311759 https://doi.org/10.3390/ijms262311759
- [3] Controlled randomised multicenter study: ChondroFiller liquid vs microfracturing for focal knee cartilage defects. (2016). https://doi.org/10.5348/VNP05-2016-1-OA-1 https://doi.org/10.5348/VNP05-2016-1-OA-1
- [4] Cartilage reconstruction using Chondrofiller in intra-articular distal radius fractures. (2025). https://doi.org/10.1186/s42836-025-00333-y https://doi.org/10.1186/s42836-025-00333-y
- [5] Influence of cartilage defects and collagen gel on intact cartilage: biomechanical in-vitro study. (2024). https://doi.org/10.1007/s00402-024-05530-z https://doi.org/10.1007/s00402-024-05530-z
- [6] Arthroscopic utilization of ChondroFiller gel for hip articular cartilage defects: 12–60-month follow-up. (2021). https://doi.org/10.1093/jhps/hnab002 https://doi.org/10.1093/jhps/hnab002
- [7] Revision rate after surgery for elbow osteochondritis dissecans: systematic review. (2025). https://doi.org/10.1186/s13018-025-05788-y https://doi.org/10.1186/s13018-025-05788-y
- [8] The role of MRI in elbow osteochondritis dissecans: correlations with intraoperative findings. (2025). https://doi.org/10.1080/15438627.2025.2487904 https://doi.org/10.1080/15438627.2025.2487904
- [9] Are Elbow Osteochondritis Dissecans Lesions Different for Gymnasts and Baseball Players?. (2025). https://doi.org/10.1097/JSM.0000000000001336 https://doi.org/10.1097/JSM.0000000000001336
Frequently Asked Questions
- Grade III–IV cartilage lesions contained within viable surrounding cartilage, with surface area no greater than 6 cm². Osteochondritis dissecans of the capitellum is the primary indication, particularly in overhead-throwing athletes and gymnasts.
- An outpatient procedure at London Cartilage Clinic taking 30–45 minutes. Ultrasound guides the needle to the lesion, and collagen is injected where it gels in 3–5 minutes. No anaesthesia or incision required.
- The scaffold's three-dimensional matrix structure acts as a chemotactic environment, drawing the patient's progenitor cells into the lesion. These cells differentiate to produce cartilage-like matrix. Ex vivo studies showed 2.4-fold DNA increase by day 14.
- No elbow-specific clinical trial exists. Evidence derives from adjacent joints: knee studies showed significant functional improvements; wrist data demonstrated superior cartilage quality. Current guidance relies on expert clinical opinion from UK specialist centres.
- ChondroFiller is an outpatient ultrasound-guided injection requiring no theatre or incision, preserving subchondral bone. Standard arthroscopic surgery carries an 11% revision rate and produces fibrocartilage. ChondroFiller targets matrix-induced chondrogenesis instead.
Next steps
Where to go from here
These routes are selected from the topic and purpose of this article. They are guidance, not a diagnosis or treatment recommendation.
Recovery route
Explore ChondroFiller recovery
Continue with practical recovery and patient-journey information.
Learn more
Explore ChondroFiller
Read the reviewed ChondroFiller pathway, including who it may help and what happens next.
Talk to the team
Book a free discovery call
A non-medical call with the team to understand services and choose the right booking route.
Legal & Medical Disclaimer
This article is written by an independent contributor and reflects their own views and experience, not necessarily those of Liquid Cartilage. It is provided for general information and education only and does not constitute medical advice, diagnosis, or treatment.
Always seek personalised advice from a qualified healthcare professional before making decisions about your health. Liquid Cartilage accepts no responsibility for errors, omissions, third-party content, or any loss, damage, or injury arising from reliance on this material.
If you believe this article contains inaccurate or infringing content, please contact us at [email protected].