
ChondroFiller injection vs hip replacement surgery
Is hip replacement your only option?
Being told you need a new hip is a significant moment, and for many patients, the assumption that follows is that surgery is the only path left. That assumption is worth examining. For selected patients with Kellgren-Lawrence Grade III or IV hip osteoarthritis, an outpatient ChondroFiller injection programme now exists as a structured, evidence-based alternative to total hip arthroplasty (THA): no operating theatre, no general or spinal anaesthesia, no surgical incision.
ChondroFiller injection is an ultrasound-guided treatment delivered at a single outpatient appointment. The injectable collagen scaffold is placed under real-time image guidance directly into the worn joint, where it gels in situ within minutes and provides a physical matrix to support the body's own repair processes. London Cartilage Clinic on Harley Street, the UK's certified delivery centre for the product, lists the hip as a clinical indication alongside seven other joints, with treatment from £3,000.
Eligibility is real and specific: the scaffold targets diffuse, advanced joint wear in patients whose hip joint can receive an injectable treatment, not only those with a single, isolated defect. The sections that follow map the procedural, practical, and clinical differences between the injection route and surgery, so patients arrive at an assessment with the right questions.
What each procedure actually involves
The procedural differences between total hip arthroplasty and a ChondroFiller injection come down to a single organising principle: surgery is subtractive, the injection is additive.
Total hip arthroplasty
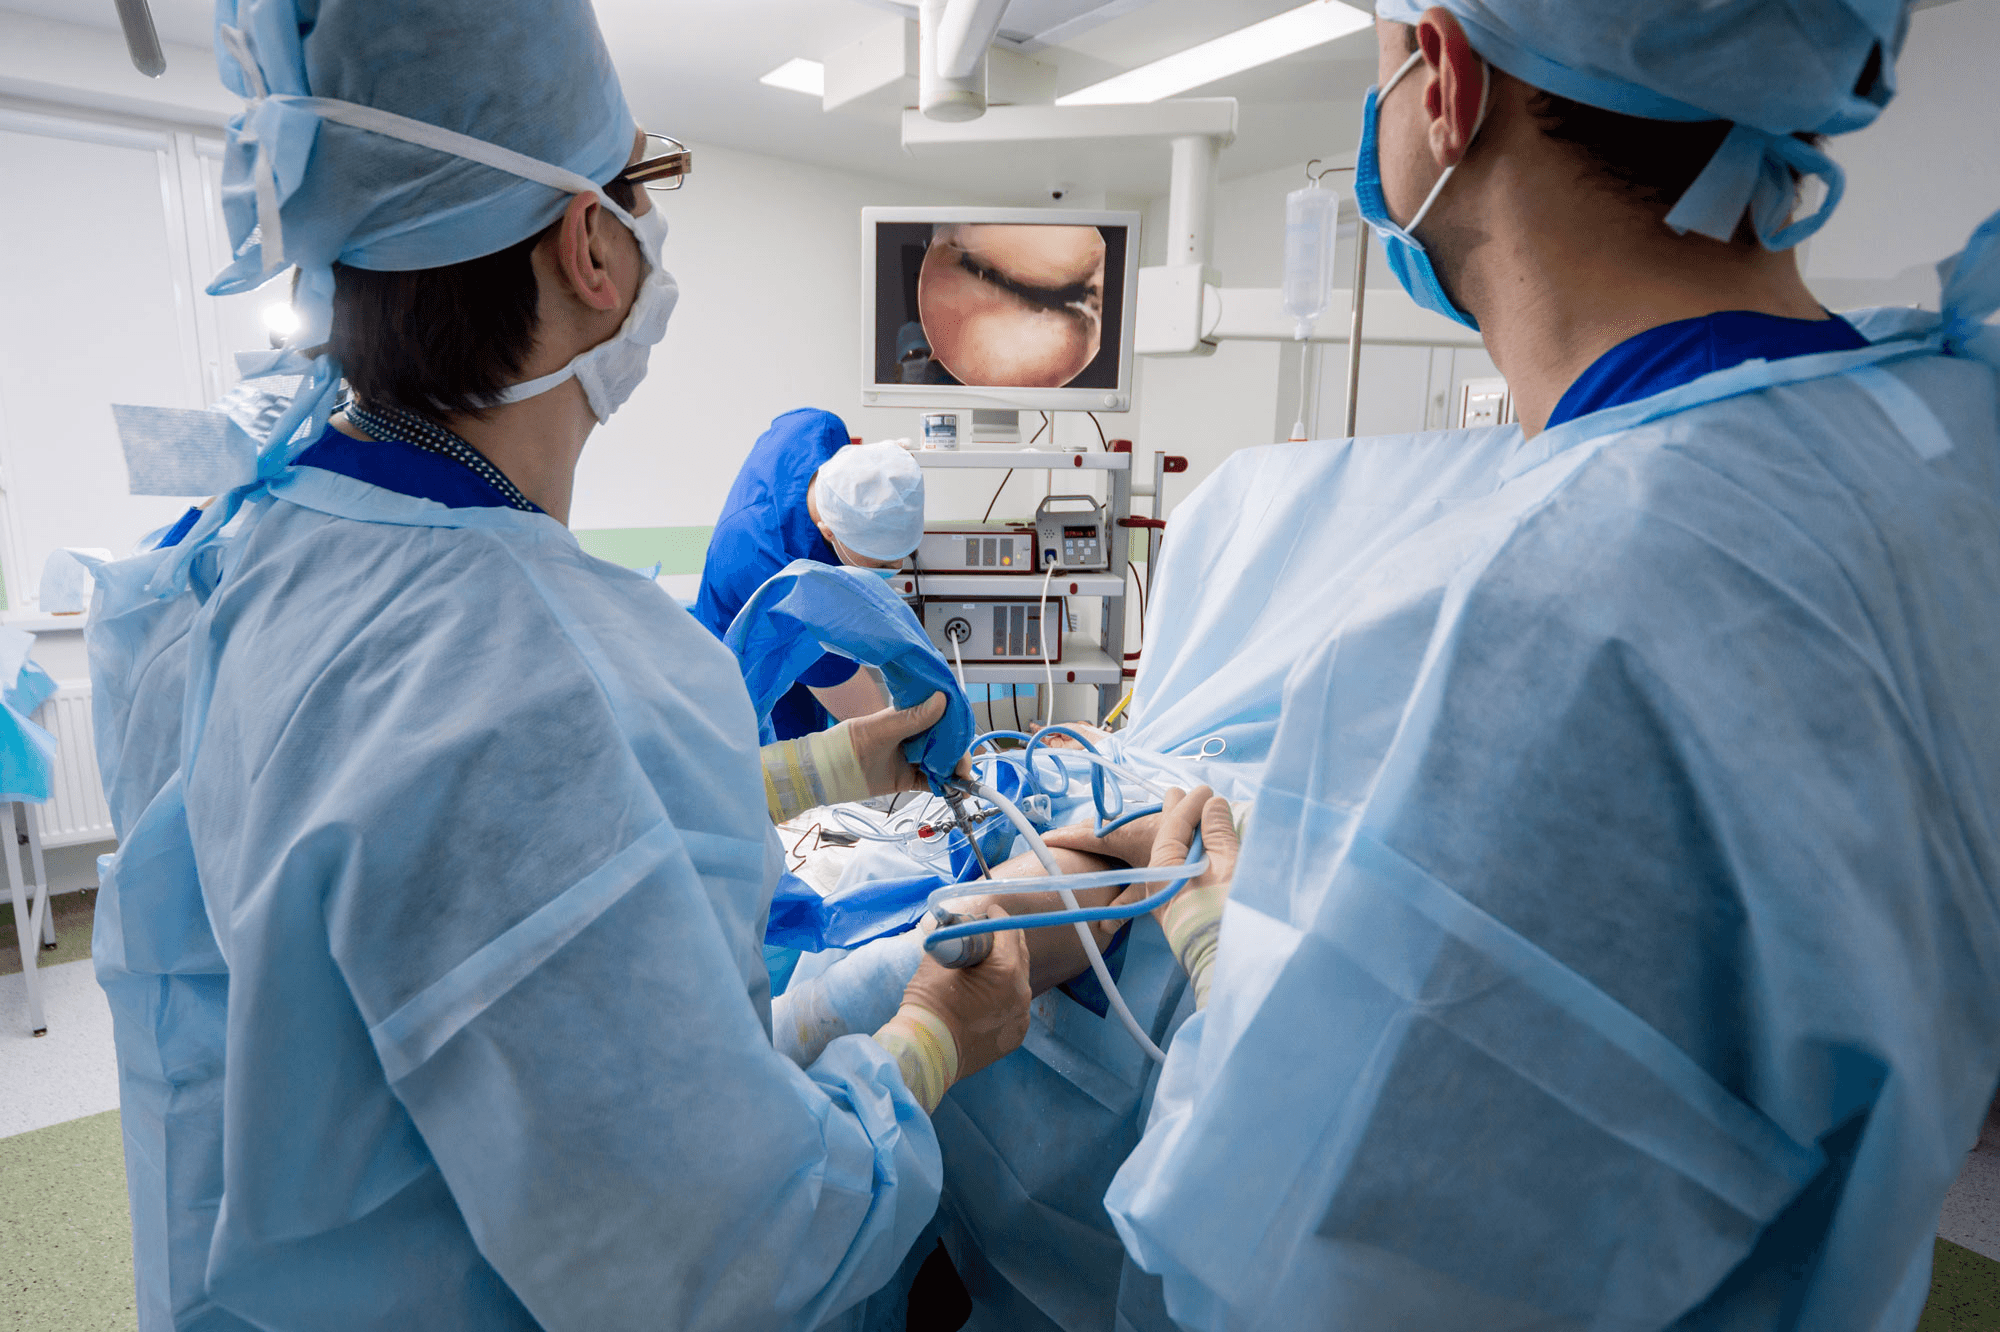
THA is a major inpatient operation performed under general or spinal anaesthesia. The surgeon makes a substantial incision, dislocates the hip, and removes, permanently, the damaged femoral head and acetabular surface. Metal and polymer components are cemented or press-fitted into the remaining bone. The patient's own joint, whatever functional tissue remains, is gone. Recovery begins in hospital and continues over several months. The intervention is irreversible.
ChondroFiller injection
The injection pathway works in the opposite direction. Rather than removing worn tissue, ChondroFiller is placed over the degenerated articular surfaces under real-time ultrasound or fluoroscopic guidance, a top-down cushion that preserves what is already there. Crucially, the injectable scaffold is formulated to polymerise within a fluid-filled joint; no surgical drying or preparation of a dry arthroscopic field is required, because the collagen gel sets within minutes in the natural synovial environment. There is no incision and no implant. The procedure is carried out at an outpatient clinic appointment; the patient leaves the same day after a short observation period with no surgical wound to manage.
Because the patient's own hip joint is never resected, additive treatment keeps all future options open, including surgery, should it ever become necessary.
How ChondroFiller injection works in the hip
The collagen scaffold is acellular, it contains no living cells. ChondroFiller works instead by providing a structured matrix that the patient's own progenitor cells can colonise, a process known as acellular matrix-induced chondrogenesis. After the gel has set within the cartilage defect, stem-like cells migrate inward from two local sources: the synovial membrane lining the joint and the subchondral bone lying just beneath the damaged surface. Over subsequent weeks and months, these recruited cells mature into chondrocytes and begin to generate repair tissue within the scaffold framework.
For the hip, this mechanism is directly relevant to the surfaces that bear the greatest mechanical load: the femoral head dome and the opposing acetabular cartilage. Published clinical work, including a 2025 case report documenting ChondroFiller application to a 15 × 5 mm osteochondral lesion at the superoanterior weight-bearing dome, confirms that the femoral head is a recognised application site and that treatment can proceed without disrupting the underlying subchondral bone through microfracture. That case report describes an arthroscopic delivery context; at London Cartilage Clinic the current service pathway is an ultrasound-guided outpatient injection, not a theatre-based procedure.
The scaffold itself is temporary by design. Over 1–2 years it is fully resorbed and replaced by the patient's endogenously generated repair tissue, leaving behind living repair cartilage rather than a permanent foreign material. This biodegradation timeline is a deliberate feature: the collagen matrix provides structural support precisely during the period when recruited cells are maturing and consolidating.
Next steps
Where to go from here
These routes are selected from the topic and purpose of this article. They are guidance, not a diagnosis or treatment recommendation.
Recovery route
Explore ChondroFiller recovery
Learn more
Explore ChondroFiller
Talk to the team
Book a free discovery call
What the clinical evidence shows
The evidence falls into three distinct tiers, and being precise about which is which is what makes this comparison clinically credible.
Knee trial data
The most rigorous controlled data come from knee studies. A 2016 multicentre RCT comparing ChondroFiller with microfracture (n=23) found significant IKDC improvement at 3, 6, and 12 months (p<0.05), with MRI confirming good defect filling, complete scaffold integration to adjacent cartilage, and zero adverse events. A 2025 prospective controlled trial (n=25, all with KL Grade IV knee OA) found that combining ChondroFiller with a mesenchymal stem cell graft produced higher KOOS scores across all subscales at 2 months than MSC injection alone, both groups achieving p<0.01 significance, with the ChondroFiller combination group pulling ahead on mean scores.
Adjacent hip injection evidence
For the hip specifically, a 2025 double-blind RCT (n=38, all patients already referred for total hip arthroplasty) using an ultrasound-guided bioengineered injection protocol produced striking results: VAS pain fell from 7.8 to 0.2, WOMAC from 76.2 to 10.5, and Harris Hip Score rose from 56.4 to 93.0 at 12 months. This study involved a different injection product, not ChondroFiller, but it establishes that injection-based hip treatment can achieve outcomes comparable to surgery in appropriately selected patients, an important proof of concept for the injection pathway as a category.
What is not yet established
There are no published randomised trials comparing ChondroFiller injection directly to total hip arthroplasty. Hip-specific ChondroFiller data currently extend to a single case-level report and extrapolation from the knee trials above. Outcomes beyond 12–24 months have not been established in either setting.
One further finding applies directly to hip loading: a 2024 in-vitro biomechanical study found that ChondroFiller did not protect opposing cartilage under immediate cyclic loading before the scaffold has stabilised. This is not a minor footnote: it is why the first weeks after an injection are paced rather than hurried, which is especially relevant in a joint that bears full body weight.
Recovery: injection pathway vs joint replacement
Recovery from total hip arthroplasty is measured in months, not weeks. Most patients are back to their usual activity through a graded return by week six, while the cartilage improvement itself, including restored walking patterns and confidence in the joint, is judged over 6 to 12 months. During the early post-operative period, hip precautions restrict certain movements to protect the new joint while soft-tissue healing occurs around the prosthesis.
The injection pathway asks for patience rather than protection. Patients walk out of the outpatient room within the hour, with no brace, and crutches or walking aids are not required unless your medical team specifies otherwise. The first three days are quiet, with ice. Weeks one and two are about half your usual joint activity while the scaffold integrates, and weeks three to six are a graded return. Physiotherapy is optional, a free six-week telephone review is included, and a 12-month MRI is reviewed with Professor Lee.
Hip patients who have read about braces, crutches and six weeks of protected weight-bearing have usually come across the other way of using the same gel. ChondroFiller can be placed by ultrasound-guided injection, as described here, or arthroscopically through the keyhole Liquid Cartilage procedure, and the two recoveries differ substantially. The brace, the protected weight-bearing and the physiotherapy-led rebuild belong to the keyhole route. The injection recovery page sets the two timelines side by side.
Two structural differences are worth stating plainly for anyone at a decision point. Hip replacement is, in most cases, a single definitive intervention, but one with a prosthetic lifespan; a proportion of younger patients will face revision surgery in later decades. The ChondroFiller injection programme is designed as an ongoing preservation pathway rather than a single curative episode, and may involve periodic follow-up injections over time. In exchange, the native joint is preserved: no prosthetic components, no revision timeline, and, critically, the option to proceed to total hip arthroplasty remains open. Choosing the injection route does not foreclose the surgical option.
Who is eligible and how to access treatment in London
The decision between these two paths ultimately rests on what a patient is willing to trade. Surgery offers a definitive structural solution, but at the cost of the native joint, irreversibly. The injection programme preserves that joint and keeps surgery available as a future option, but requires honest acceptance of an evolving evidence base, a paced return to activity over the first six weeks, and the likelihood of periodic follow-up rather than a single endpoint.
In terms of who is eligible for ChondroFiller injection: the clinical indication covers diffuse cartilage wear at Kellgren-Lawrence Grade III or IV, the same population typically referred for total hip arthroplasty. Individual suitability, including joint geometry and structural integrity, is confirmed at assessment. Patients with severe deformity requiring structural correction may not be candidates for an injectable pathway.
Treatment is self-funded private only; it is not currently available on the NHS or through standard private medical insurance. Guide pricing at London Cartilage Clinic starts from £3,000 for a single injection; the full programme cost depends on the treatment tier and number of joints, confirmed at consultation.
Liquid Cartilage™ is delivered in the UK at the London Cartilage Clinic on Harley Street. Assessment bookings can be made at londoncartilage.com.
- [1] Nanosurgery and Bioengineered Regenerative Protocols for the Treatment of Hip Osteoarthritis: A Double-Blind Randomized Controlled Trial as an Alternative to Surgical Hip Replacement. (2025). https://doi.org/10.3390/biomedicines13040987 https://doi.org/10.3390/biomedicines13040987
- [2] Joint Preservation in Patients with Grade IV Osteoarthritis of the Knee: Use of an Acellular Collagen Scaffold (ChondroFiller® Liquid) and Blood Derived Stem Cell Rich Graft, A Prospective Controlled Trial. (2025). https://doi.org/10.29011/2575-9760.011360 https://doi.org/10.29011/2575-9760.011360
- [3] Implantation of ChondroFiller Liquid® as a Scaffold Material for the Treatment of Chondral Lesions of the Knee Joint. (2024). https://doi.org/10.5272/jimab.2024304.5936 https://doi.org/10.5272/jimab.2024304.5936
- [4] Hip Arthroscopy and Chondrofiller Application in Isolated Osteochondral Defect of the Femoral Head. (2025). https://doi.org/10.13107/jocr.2025.v15.i10.6176 https://doi.org/10.13107/jocr.2025.v15.i10.6176
- [5] Cartilage reconstruction using Chondrofiller in intra-articular distal radius fractures. (2025). https://doi.org/10.1186/s42836-025-00333-y https://doi.org/10.1186/s42836-025-00333-y
- [6] Influence of cartilage defects and a collagen gel on integrity of corresponding intact cartilage: a biomechanical in-vitro study. (2024). https://doi.org/10.1007/s00402-024-05530-z https://doi.org/10.1007/s00402-024-05530-z
- [7] Controlled, randomized multicenter study to compare compatibility and safety of ChondroFiller liquid with microfracturing of patients with focal cartilage defects of the knee joint. (2016). https://doi.org/10.5348/VNP05-2016-1-OA-1 https://doi.org/10.5348/VNP05-2016-1-OA-1
Frequently Asked Questions
- ChondroFiller is an ultrasound-guided outpatient injection of collagen scaffold placed over damaged hip surfaces. Unlike hip replacement, which removes tissue, ChondroFiller adds a protective matrix that preserves your native joint.
- Patients with diffuse, advanced hip wear at Kellgren-Lawrence Grade III or IV osteoarthritis. Your individual suitability, including joint geometry and structural integrity, is confirmed during assessment.
- You walk out the same hour, with no brace, and crutches are not required unless your medical team specifies otherwise. Expect quiet first three days, about half your usual joint activity in weeks one and two, then a graded return by week six. Physiotherapy is optional. The six weeks of protected weight-bearing you may have read about belongs to the arthroscopic (keyhole) route, not the injection.
- Yes. Because ChondroFiller preserves your native joint tissue, hip replacement remains available as a future option if needed. The injection procedure is reversible in this way.
- Treatment is private only, starting from £3,000 for a single injection. The full programme cost depends on your treatment tier and number of joints, confirmed during consultation.
Next steps
Where to go from here
These routes are selected from the topic and purpose of this article. They are guidance, not a diagnosis or treatment recommendation.
Recovery route
Explore ChondroFiller recovery
Continue with practical recovery and patient-journey information.
Learn more
Explore ChondroFiller
Read the reviewed ChondroFiller pathway, including who it may help and what happens next.
Talk to the team
Book a free discovery call
A non-medical call with the team to understand services and choose the right booking route.
Legal & Medical Disclaimer
This article is published by Liquid Cartilage for general information and education only. It does not constitute medical advice, diagnosis, or treatment.
Always seek personalised advice from a qualified healthcare professional before making decisions about your health. Liquid Cartilage accepts no responsibility for errors, omissions, third-party content, or any loss, damage, or injury arising from reliance on this material.
If you believe this article contains inaccurate or infringing content, please contact us at [email protected].