
ChondroFiller injection vs Arthrosamid
Why the MRI decides, not the pain score
Comparing ChondroFiller injection and Arthrosamid often leads patients to ask the wrong question. The instinct is to weigh them against each other — to ask which is more effective, or which lasts longer. Neither question gets to the point, because these two treatments are not competing answers to the same problem. They address structurally different forms of joint damage, and no amount of pain severity tells a clinician which one is needed.
ChondroFiller injection is designed for a discrete, focal cartilage defect — a localised patch of cartilage loss in a joint that is otherwise in reasonable condition. Think of it as filling a pothole: the surrounding road is intact, and the repair targets the specific cavity. Arthrosamid works on an entirely different structure. Rather than addressing a focal cartilage pit, it integrates into the synovial membrane — the joint lining — to cushion and dampen inflammation across a joint with widespread, diffuse osteoarthritis. That is a road in need of resurfacing, not a single repair.
Symptom severity alone cannot distinguish these two presentations. A patient with a painful focal defect and a patient with global Kellgren-Lawrence Grade 2–3 osteoarthritis may report similar pain levels, yet the appropriate intervention is different in each case. MRI is the clinical gate. The imaging report will typically show whether there is a localised full-thickness cartilage lesion or diffuse joint-space narrowing and degeneration — and that structural finding, not the pain score, is what guides the treatment discussion.
How ChondroFiller injection works
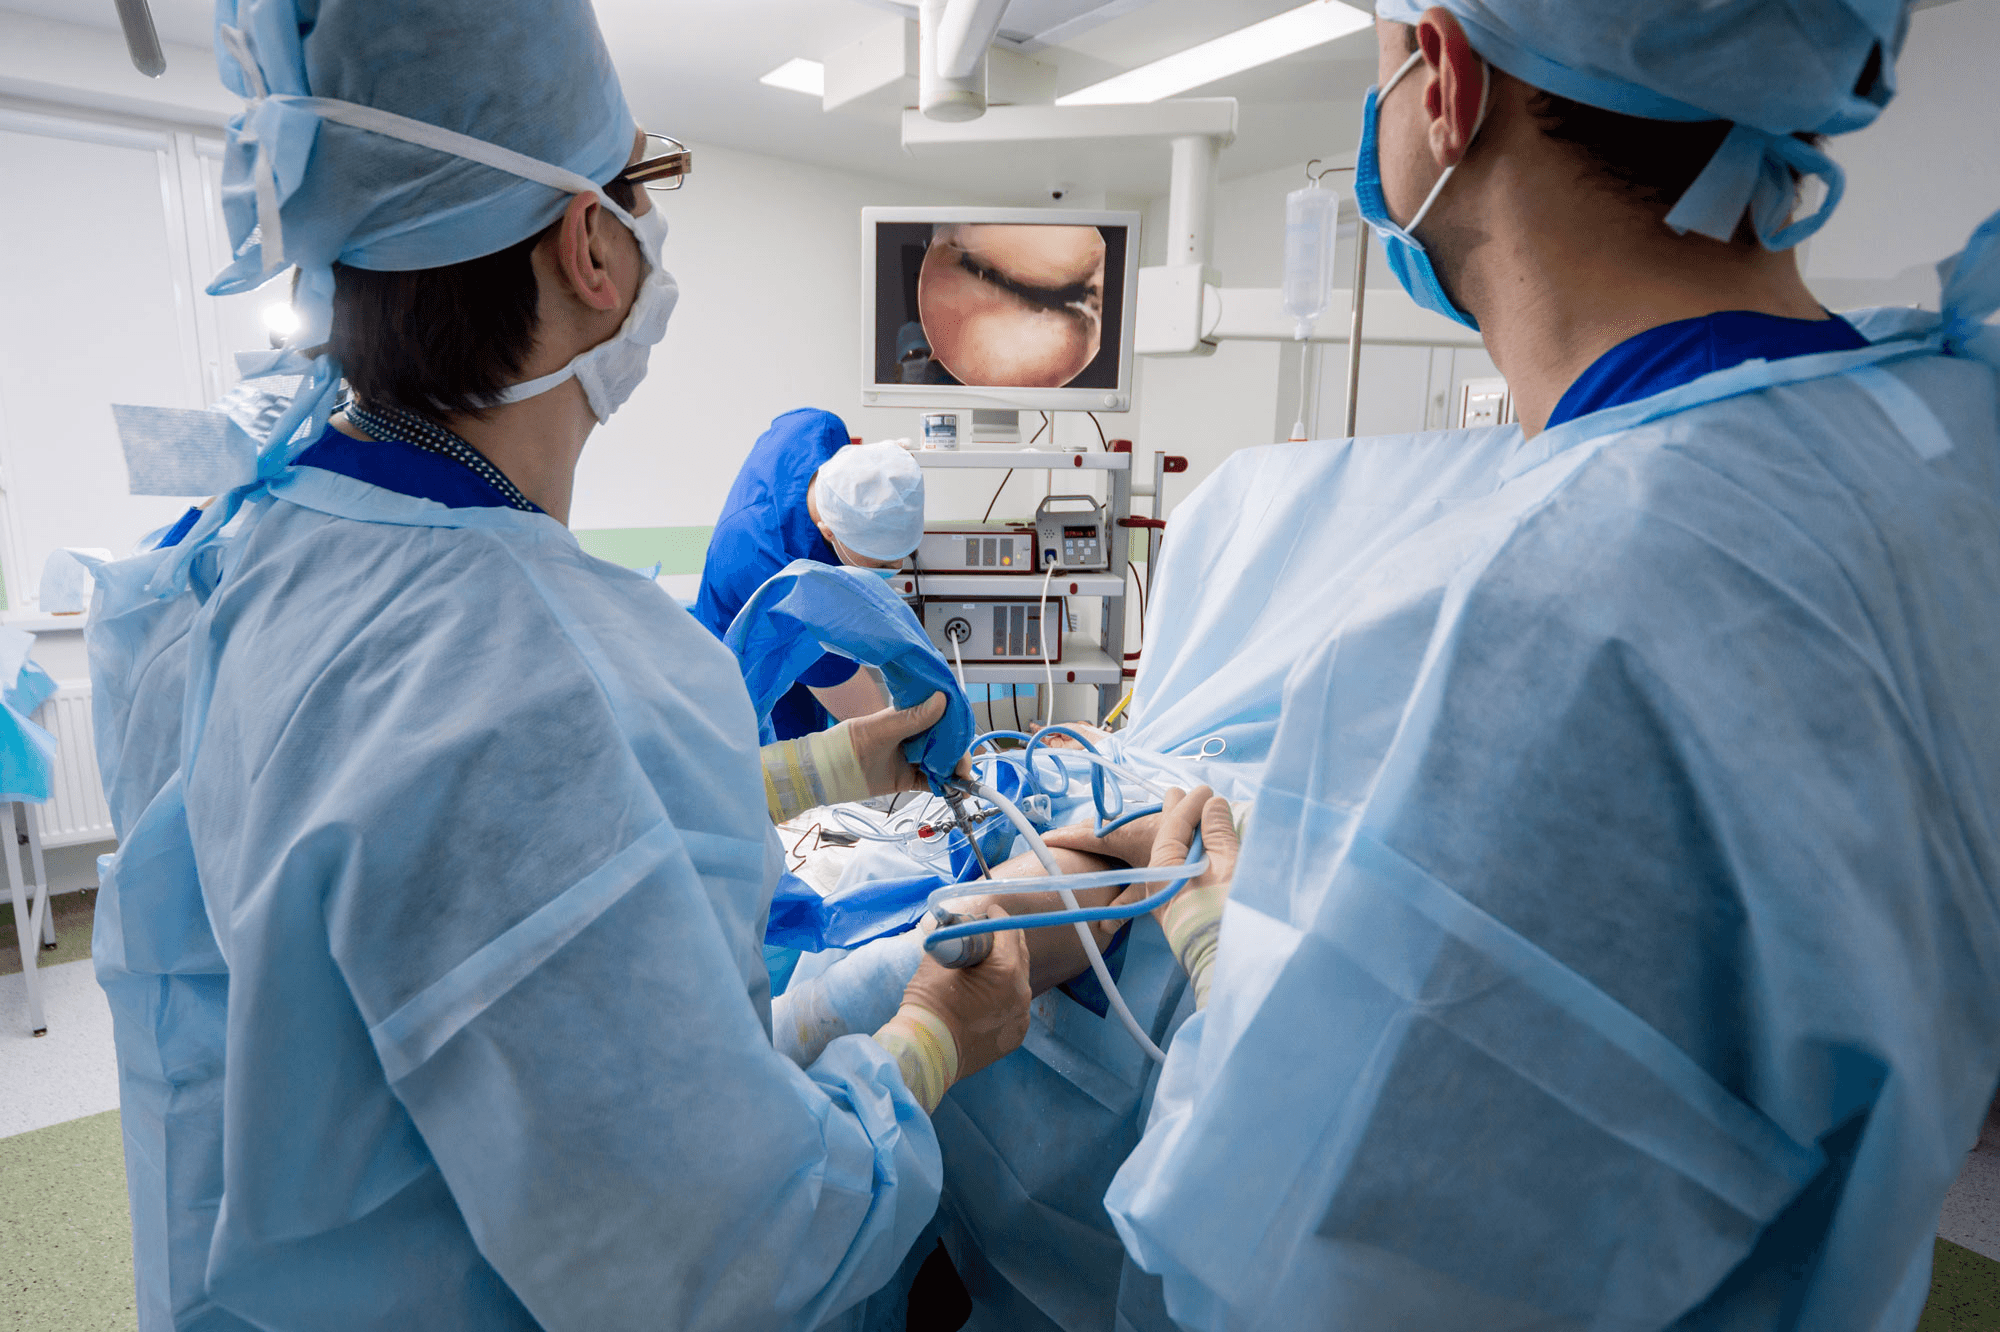
The ChondroFiller injection itself is a liquid — a clear, acellular Type I collagen hydrogel placed under ultrasound guidance directly into the cartilage defect during a standard outpatient appointment. No theatre, no general anaesthetic, no incisions. Within 3–5 minutes of injection, the collagen sets in place, filling the cavity and forming a stable three-dimensional matrix.
What follows is where the biology is worth understanding. The scaffold contains no donor cells. It works through matrix-induced chondrogenesis: the collagen structure acts as a chemotactic environment, drawing in the patient's own progenitor cells from the surrounding synovium and subchondral bone. Those cells migrate into the matrix and begin producing repair tissue. An ex vivo osteochondral model recorded a 2.4-fold increase in DNA content within the scaffold by day 14, which under laboratory conditions corroborates this recruitment process. What unfolds inside a living joint will vary with defect size, local tissue biology, and the mechanical environment of the joint — these are the factors that make patient selection matter as much as the treatment itself.
Over the following 12–24 months, the collagen scaffold gradually resorbs as host repair tissue replaces it. Early load management is part of this process. A biomechanical cyclic-loading study found that the scaffold offers no protective advantage under full weight-bearing before it has stabilised, which is why a period of restricted weight-bearing follows the injection — not as a precaution, but as a practical requirement for the repair tissue to establish itself.
How Arthrosamid works
Arthrosamid (Contura International) is a 6 mL single-dose injection of 2.5% cross-linked polyacrylamide suspended in 97.5% sterile water. Once injected into the knee joint under ultrasound guidance, it integrates permanently into the synovial membrane — the joint lining — where it provides mechanical cushioning, reduces friction, and dampens inflammatory signalling. It is non-biodegradable: unlike the collagen scaffold described in the previous section, it does not resorb over time or give way to host tissue. It does not regenerate or scaffold cartilage; that is not what it is designed to do.
The durability evidence is reasonably encouraging for a non-surgical treatment. In a 150-patient retrospective cohort (Kellgren-Lawrence Grade II–IV), Arthrosamid maintained slight VAS pain improvement at 12 months, while patients in the hyaluronic acid and corticosteroid groups had returned to near-baseline scores by that point (iPAAG was superior to steroid at 6 months, p<0.001, though not significantly different from HA at 12 months, p=0.128). A three-year prospective multicentre study conducted in Denmark showed sustained WOMAC improvement in pain, stiffness, and function through 36 months. A systematic review of 463 patients confirmed significant outcomes through two years, with no long-lasting adverse events reported.
Certain presentations are contraindicated: inflammatory arthritis (including rheumatoid arthritis and gout), end-stage Kellgren-Lawrence Grade 4 osteoarthritis where joint replacement is the clinically appropriate pathway, active joint infection, and known hypersensitivity to polyacrylamide. Identifying these exclusions early is useful groundwork for patients before any clinical consultation.
Candidate profiles: who suits each treatment
Matching the right injection to the right joint hinges on one structural question: is the cartilage damage focal or global?
ChondroFiller injection
The ChondroFiller injection is designed for discrete, containable damage — a focal Grade III–IV lesion in an otherwise workable joint, typically up to 3 cm² in area (extendable to 6 cm² where anatomy permits). The surrounding tissue needs to be viable: the scaffold's cell-recruitment mechanism relies on progenitor cells from the adjacent synovium and subchondral bone, so those structures must be in reasonable condition. Stable joint mechanics and absence of significant malalignment are prerequisites.
Age is less a barrier than overall joint health. Younger and active patients with post-traumatic lesions are a classic fit, but so are selected older patients where a genuine focal defect exists in an otherwise preserved joint. What removes patients from contention is diffuse OA in the surrounding tissue. In a hip arthroscopy cohort, 17 of 21 followed patients with isolated defects achieved good or excellent results at 3–5 years; those with pre-existing Tönnis Grade 2–3 osteoarthritis had poor outcomes. The state of the surrounding joint, not just the defect itself, determines suitability.
Arthrosamid
Arthrosamid suits the opposite clinical pattern: diffuse, global joint degeneration at Kellgren-Lawrence Grade 2–3, where pain originates from the joint environment rather than a single reparable lesion. It is not the right choice where an isolated, containable defect is the primary finding — nor where inflammatory arthritis, Grade 4 end-stage disease, active joint infection, or polyacrylamide allergy is present.
No direct trial comparison
No published head-to-head RCT has compared these two treatments. The evidence for each runs on separate clinical tracks, which reflects the fact that they address anatomically distinct problems. Selecting between them — or combining them in a dual-target protocol — rests on imaging findings and clinical assessment, not on comparative trial data.
When both are used together
Some presentations combine both problems — a focal cartilage defect at the bone surface alongside diffuse synovial involvement in the same joint. In selected patients at Kellgren-Lawrence Grade III or IV, clinicians may administer both injections within a single session under ultrasound guidance: ChondroFiller injection (2.3 mL) targeting the bone-end cartilage defect, and Arthrosamid (6 mL) integrating into the synovial lining. These are not mixed together or used as one product; each has a separate anatomical target and a separate mechanism, as set out in the preceding sections. The combined protocol is referred to clinically as CFI+ and is priced at approximately £6,000.
The mechanistic rationale is straightforward — the joint has two co-existing problems, each addressed by the appropriate tool. What controlled trial data do not yet confirm is whether the combined outcome exceeds each component's individual benefit; this remains a clinically described approach rather than an established evidence-based standard.
Suitability for CFI+ depends on the individual justification for each component separately. Inflammatory arthritis, active infection, or polyacrylamide allergy would exclude the Arthrosamid element; absent a genuine focal defect with viable surrounding tissue, ChondroFiller injection adds nothing. Both conditions must be present and individually indicated for the combination to make clinical sense.
What to expect at assessment and how to access treatment
The starting point is an MRI of the affected joint. Imaging characterises whether cartilage loss is focal or diffuse — the structural distinction that determines which pathway applies. Once that is established, a clinical assessment can match the treatment to the finding.
On cost: both treatments start from approximately £3,000. The ChondroFiller injection is volume-dependent and may reach approximately £8,000 for larger defects; the CFI+ dual-injection combination, where both components are individually indicated, is priced at approximately £6,000.
On evidence: injection-specific long-term data for ChondroFiller extend to around five years; if a 10-year dataset is what you need before acting, that data does not yet exist for the injectable route. Sub-group MCID data from 2025 Arthrosamid cohorts are still being published. For most patients considering these options, the available evidence is sufficient to frame a decision — and a structured clinical assessment is exactly what is designed to work through the outstanding questions alongside your imaging and history.
Liquid Cartilage™ (ChondroFiller injection) is delivered in the UK at the London Cartilage Clinic on Harley Street by Professor Paul Y. F. Lee. Book a clinical assessment at londoncartilage.com.
- [1] A Systematic Review of Arthrosamid Polyacrylamide (PAAG) Hydrogel for Treatment of Knee Osteoarthritis. (2022). https://doi.org/10.18103/mra.v10i8.2950 https://doi.org/10.18103/mra.v10i8.2950
- [2] Arthroscopic utilisation of ChondroFiller gel for hip articular cartilage defects: 12–60 month follow-up. (2021). https://doi.org/10.1093/jhps/hnab002 https://doi.org/10.1093/jhps/hnab002
- [3] Comparative efficacy of polyacrylamide hydrogel versus hyaluronic acid and corticosteroids in knee osteoarthritis: retrospective cohort. (2025). https://doi.org/10.1097/MD.0000000000044655 https://doi.org/10.1097/MD.0000000000044655
- [4] Influence of cartilage defects and collagen gel on integrity of intact cartilage: biomechanical in-vitro study. (2024). https://doi.org/10.1007/s00402-024-05530-z https://doi.org/10.1007/s00402-024-05530-z
- [5] Ex Vivo Osteochondral Biomimetic Platform for Mechanistic Investigation of Cartilage Regeneration. (2025). https://doi.org/10.3390/ijms262311759 https://doi.org/10.3390/ijms262311759
- [6] AB1185 Polyacrylamide Hydrogel for Knee OA: 3-year follow-up of a prospective clinical study (EULAR 2023). (2023). https://doi.org/10.1136/annrheumdis-2023-eular.6038 https://doi.org/10.1136/annrheumdis-2023-eular.6038
Frequently Asked Questions
- ChondroFiller targets focal cartilage defects in otherwise healthy joints; Arthrosamid addresses diffuse joint degeneration via the synovial membrane. MRI imaging, not pain severity, determines which is appropriate.
- ChondroFiller is an acellular Type I collagen scaffold injected directly into the defect. It recruits the patient's own progenitor cells, which migrate into the scaffold and generate repair tissue whilst the collagen gradually resorbs over 12–24 months.
- Arthrosamid integrates permanently into the synovial lining to provide mechanical cushioning, reduce friction, and dampen inflammation throughout the joint. It does not regenerate cartilage.
- Yes. In selected patients at Kellgren-Lawrence Grade III–IV, both may be injected in one session (CFI+): ChondroFiller for the focal defect, Arthrosamid for the synovial lining. CFI+ costs approximately £6,000.
- ChondroFiller starts from approximately £3,000, rising to approximately £8,000 for larger defects. Arthrosamid starts from approximately £3,000. The combined CFI+ treatment costs approximately £6,000.
Next steps
Where to go from here
These routes are selected from the topic and purpose of this article. They are guidance, not a diagnosis or treatment recommendation.
Learn more
Explore Arthrosamid
Read the reviewed Arthrosamid pathway, including who it may help and what happens next.
Learn more
Explore ChondroFiller
Read the reviewed ChondroFiller pathway, including who it may help and what happens next.
Talk to the team
Book a free discovery call
A non-medical call with the team to understand services and choose the right booking route.
Legal & Medical Disclaimer
This article is written by an independent contributor and reflects their own views and experience, not necessarily those of Liquid Cartilage. It is provided for general information and education only and does not constitute medical advice, diagnosis, or treatment.
Always seek personalised advice from a qualified healthcare professional before making decisions about your health. Liquid Cartilage accepts no responsibility for errors, omissions, third-party content, or any loss, damage, or injury arising from reliance on this material.
If you believe this article contains inaccurate or infringing content, please contact us at [email protected].