
ChondroFiller injection for thumb and small hand joints
Filling the gap between painkillers and thumb surgery
Grip weakens. Pinch hurts. Opening a jar, turning a key, or pressing a thumb against a phone screen becomes something you plan around rather than do automatically. For the roughly 30% of postmenopausal women who develop basal thumb arthritis — wear and tear at the trapeziometacarpal joint where the thumb meets the wrist — this is a familiar and frustrating plateau.
The standard conversation at that point tends to offer two options. The first is continued pain management: anti-inflammatories, splinting, steroid injections that may help for a time but do not alter the underlying cartilage loss. The second is trapeziectomy — a well-established surgical procedure that removes the trapezium bone entirely and reconstructs the joint. Trapeziectomy has a strong long-term record, but it is irreversible, carries a meaningful recovery period, and many patients reach their consultant not yet ready for that step, or not yet at the clinical threshold where it would be recommended.
The gap between those two positions — confirmed OA on imaging, pain limiting daily function, but no indication yet for joint reconstruction — is exactly where a ChondroFiller injection is designed to sit. Delivered as an outpatient procedure under image guidance, it places an injectable collagen scaffold directly into the focal cartilage defect within the joint. The scaffold is not a painkiller, and it is not a lubricant: it is a regenerative matrix intended to support structural repair at the site of damage, rather than simply managing symptoms around it. For patients in this intermediate window, it offers a minimally invasive option that does not foreclose the surgical route should it ever be needed.
How the scaffold works inside a small joint
The collagen scaffold that makes up ChondroFiller is acellular — it contains no donor cells, no harvested tissue, and requires no biopsy. What it contains instead is a structured collagen type I matrix that, once injected into the defect, sets in place within minutes and begins signalling the surrounding biology.
That signal is chemotactic: the scaffold draws the patient's own mesenchymal stem cells and chondrocytes inward from the adjacent synovial tissue and subchondral bone. An ex vivo study measured a 2.4-fold increase in DNA content within the scaffold by day 14 — direct evidence that this recruitment is not theoretical but active and quantifiable. The cells that arrive are the patient's own; the scaffold provides the structured environment in which they can settle and begin to build.
As those recruited cells lay down new cartilage matrix, the collagen scaffold is gradually resorbed. The aim is for the defect space to be occupied by repair tissue generated through the patient's own biology, rather than by an implanted substitute that remains in place indefinitely.
Because the mechanism is patient-driven rather than joint-specific, it is not in principle confined to large joints. The CE mark covers focal articular cartilage defects across joints. In the geometrically confined space of the thumb and small hand joints, it also matters that the material self-conforms on injection — setting to the exact shape of the defect without pre-shaped implants — which makes accurate, flush-level placement both achievable and, in constricted anatomy, technically demanding.
What the thumb OA evidence shows
Published in 2023, a prospective study by Corain et al. provides the most direct clinical evidence for ChondroFiller injection at the trapeziometacarpal joint. Forty-three patients with Eaton-Littler Stage I–IV basal thumb OA received a single image-guided ChondroFiller injection and were followed at 30 days and six months. The study used established upper-limb outcome measures throughout: NRS pain scoring, DASH functional questionnaire, and objective strength testing via Jamar grip and pinch dynamometry.
Both cohorts — early-stage (Stages I–II) and advanced-stage (Stages III–IV) — recorded significant improvements in NRS pain and DASH scores at both follow-up timepoints. Crucially, those gains were not confined to self-reported measures: grip and pincer strength improved on objective testing, which matters clinically because functional hand strength is what determines whether patients can manage daily tasks independently.
Post-treatment MRI added a structural dimension to the findings. Imaging demonstrated reduced bone marrow oedema, diminished periarticular effusion, and visible joint-space widening — changes that suggest something beyond simple pain modulation and point toward a biological response at the joint level.
The Stage III–IV findings deserve specific attention. Advanced trapeziometacarpal OA is conventionally treated as a contraindication to cartilage-restoration approaches on the basis that the joint is too far degenerated to benefit. The Corain data challenge that assumption, but the challenge is provisional: this is a single prospective study with six-month follow-up and no randomised control group. The Stage III–IV results are promising, and they warrant larger series and longer observation before they could reasonably change clinical selection criteria.
Wrist and other small hand joint defects
The wrist presents a different clinical scenario from the thumb: cartilage damage here most commonly follows trauma, particularly intra-articular fractures of the distal radius that leave residual chondral defects once the bone has been stabilised. A 2025 prospective study by Demmer et al. (PMC12498443) examined ChondroFiller in exactly this setting — residual chondral defects of 0.5–2 mm in 25 of 59 patients undergoing arthroscopy-assisted open reduction and internal fixation. This is a surgical research context rather than the current outpatient injection pathway, but its findings carry a practical lesson that applies regardless of delivery route.
At second-look arthroscopy, treated defects showed significantly better cartilage quality than untreated controls: median ICRS grade 1 versus 3 (P=0.002) and Outerbridge score 1.5 versus 3 (P=0.006). Only 0.2–0.3 mL of the 1 mL preparation was needed per site, delivered through fine-gauge G20–21 cannulas — a reminder of how little volume small joint spaces can accommodate.
The most technically consequential finding concerned fibrous tissue formation. It occurred exclusively in defects that had been overfilled; applications placed flush to the surrounding cartilage surface produced none. In a geometrically constricted joint where adjacent articular surfaces are close and volume tolerances are small, this makes precise volumetric fill the dominant technical variable — more so than in larger joints where marginal overspill carries fewer consequences.
Direct outpatient injection evidence in small hand and wrist joints remains at an earlier stage than the data available for the knee or hip, and the thumb OA findings discussed above represent the strongest upper-limb clinical series to date.
Who is and isn't a candidate
Assessment for a ChondroFiller injection in the thumb or small hand joints centres on defect morphology above all else. The treatment is designed for focal, contained cartilage lesions — defects with clear, well-defined edges and healthy surrounding cartilage intact on both sides of the joint. When that surrounding tissue is compromised, or wear is diffuse across the joint surface rather than discrete and bounded, the biological conditions that allow the scaffold to integrate are absent.
For the trapeziometacarpal joint, Corain et al.'s data span Eaton-Littler Stages I through IV, which suggests the approach is not limited to the earliest disease stages alone. The Stage III–IV picture is examined in detail earlier in this article; it remains a promising signal rather than confirmed protocol.
The clearest exclusion is Kellgren-Lawrence Grade IV OA — end-stage diffuse degeneration that has moved well beyond what a focal scaffold can address. This rule holds across all joints treated with ChondroFiller, and evidence from hip applications makes the reasoning concrete: a prospective cohort of patients receiving ChondroFiller for hip cartilage defects found that those with Tönnis Grade 2–3 background osteoarthritis achieved poor outcomes even where a focal defect had been directly treated. Advanced pre-existing degeneration across the joint is not a passive bystander — it undermines what any scaffold can accomplish at a specific site.
One post-procedure consideration applies regardless of which small hand joint is treated. A biomechanical study found that during the early period after placement — before the gel has reached stable integration — the scaffold cannot protect opposing cartilage surfaces under cyclic loading. Restricting pinch and grip force during this integration window is therefore a precaution built into the recovery plan, not a sign of a complication.
Getting assessed and treated in London
The evidence base for thumb and small hand joint applications is promising but at an earlier stage than for the knee or hip — there are no large randomised trials, no long-term follow-up data for upper-limb uses, and no NICE appraisal to date. That context belongs at the front of any conversation about access and next steps, not at the back.
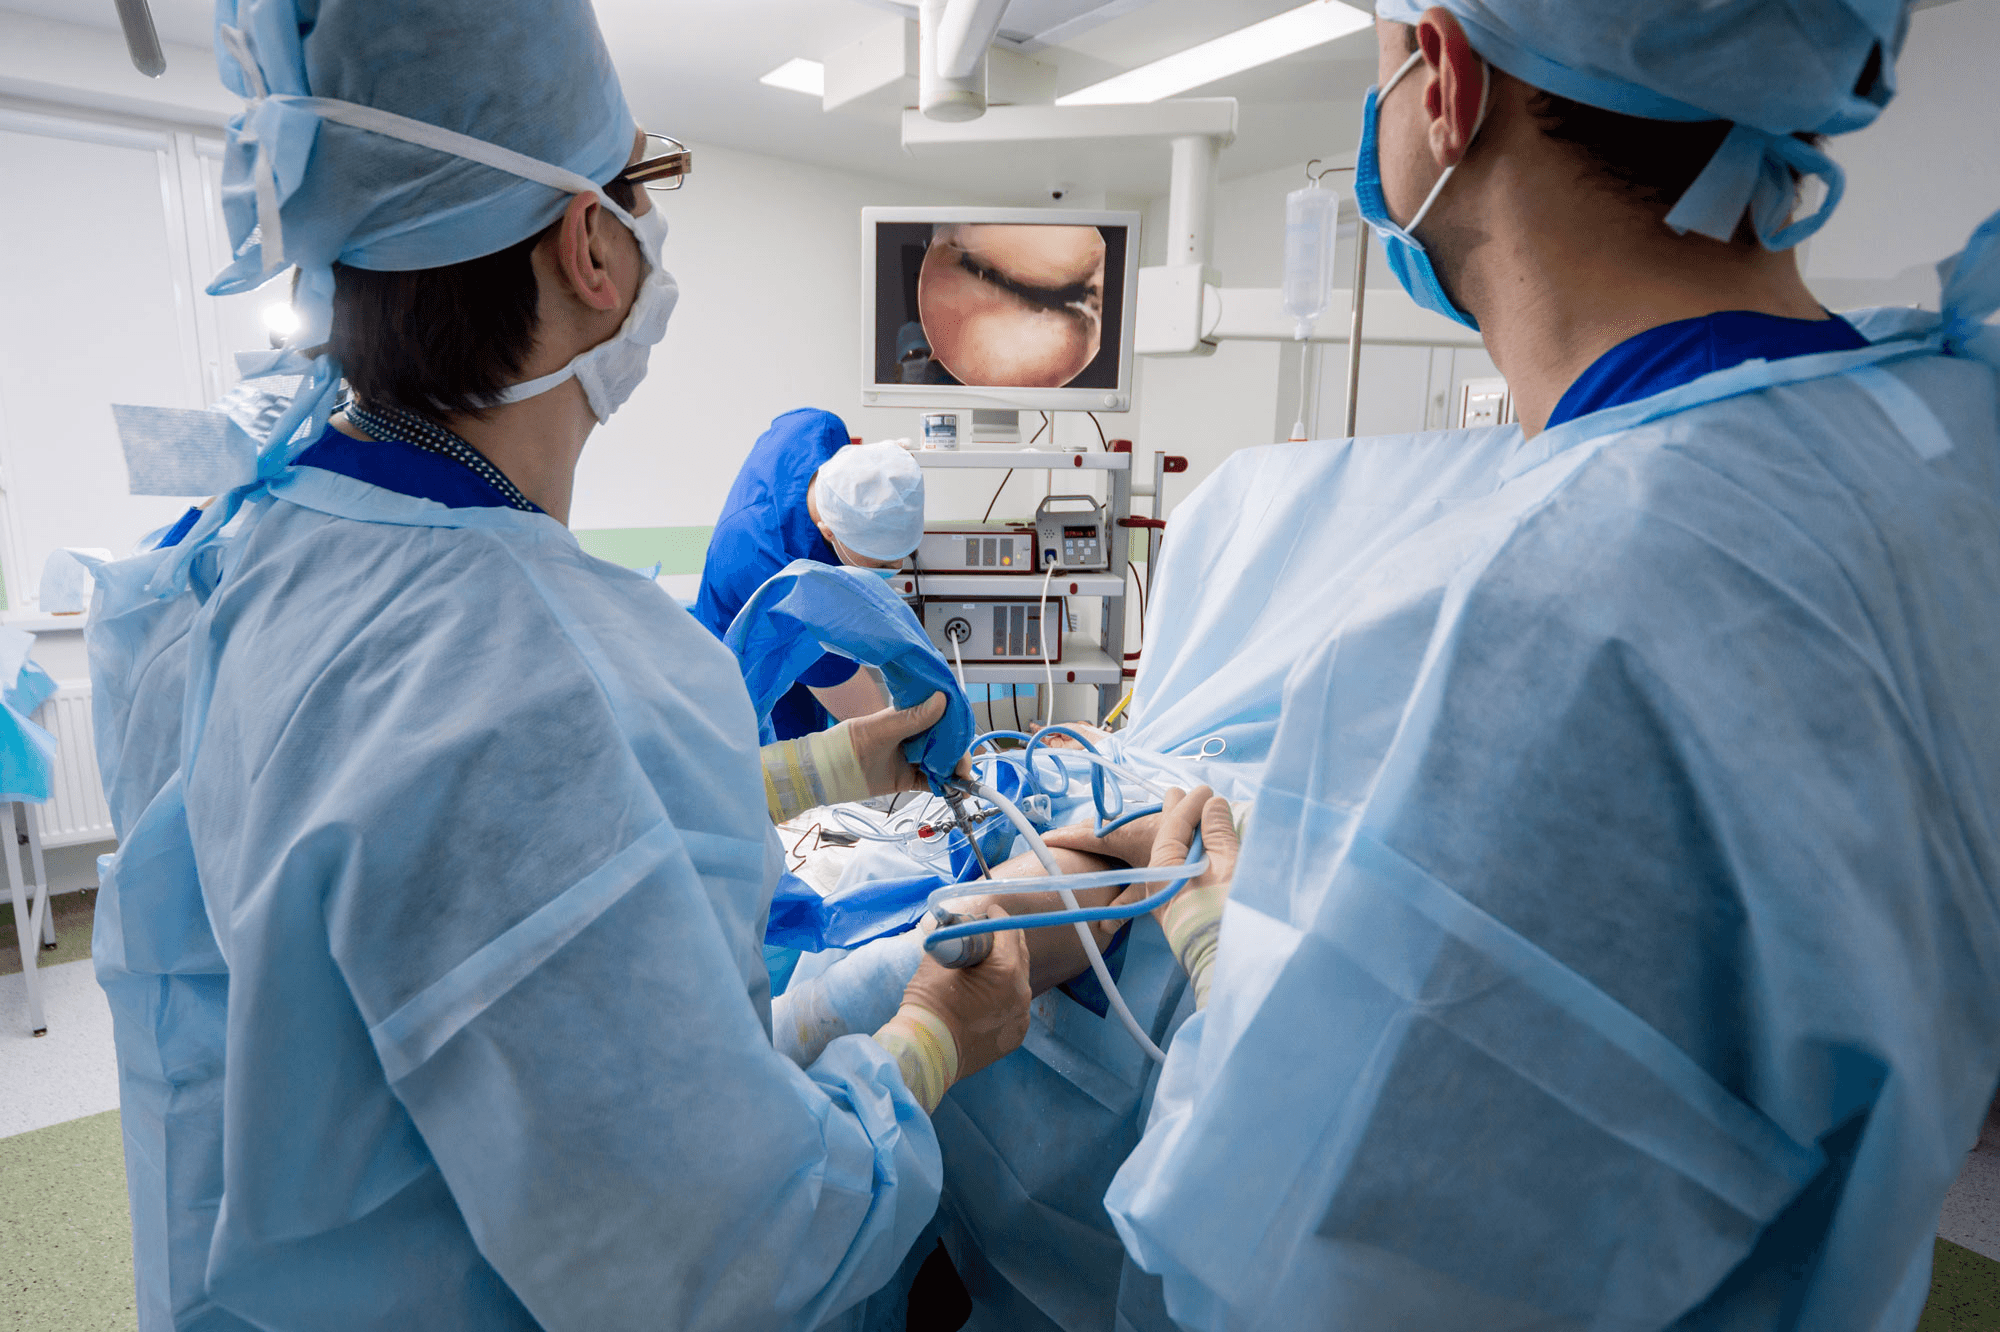
For patients in whom a focal, contained defect has been confirmed on imaging, ChondroFiller injection is delivered as an outpatient procedure under image guidance — no general anaesthetic, no surgical incision, no theatre admission. The assessment appointment reviews current imaging, maps the defect morphology, and establishes whether this pathway is appropriate or whether a different route better fits the clinical picture. Not every referral will end in an injection; for some patients, the assessment will point elsewhere.
In the UK, Liquid Cartilage™ is delivered at the London Cartilage Clinic on Harley Street — the certified UK centre for this treatment. Professor Paul Y. F. Lee leads delivery; in geometrically demanding joints such as the thumb and wrist, the precision of placement shapes what the scaffold can achieve.
To book an assessment, visit londoncartilage.com.
- [1] Ex Vivo Osteochondral Biomimetic Platform for Mechanistic Investigation of Cartilage Regeneration. (2025). https://doi.org/10.3390/ijms262311759 https://doi.org/10.3390/ijms262311759
- [2] Cartilage reconstruction using Chondrofiller in intra-articular distal radius fractures. (2025). https://doi.org/10.1186/s42836-025-00333-y https://doi.org/10.1186/s42836-025-00333-y
- [3] Arthroscopic utilisation of ChondroFiller gel for hip cartilage defects: 12–60 month follow-up. (2021). https://doi.org/10.1093/jhps/hnab002 https://doi.org/10.1093/jhps/hnab002
- [4] Influence of cartilage defects and collagen gel on intact cartilage: biomechanical in-vitro study. (2024). https://doi.org/10.1007/s00402-024-05530-z https://doi.org/10.1007/s00402-024-05530-z
Frequently Asked Questions
- ChondroFiller is an injectable collagen scaffold placed into focal cartilage defects under image guidance. It recruits the patient's own mesenchymal stem cells to the site, supporting structural cartilage repair rather than simply managing pain.
- A 2023 prospective study of 43 patients showed significant improvement in pain, hand function scores, and grip/pinch strength at six months, with MRI evidence of reduced bone marrow oedema and joint-space widening across early and advanced disease stages.
- Patients with focal, contained cartilage lesions—clearly defined defects with healthy surrounding cartilage on both sides. Advanced Kellgren-Lawrence Grade IV osteoarthritis is an exclusion; the injection targets specific damage, not diffuse joint wear.
- Unlike painkillers, it targets cartilage repair structurally. Unlike trapeziectomy (joint reconstruction), it is minimally invasive, outpatient, and reversible—offering an intermediate option for patients not yet ready for or suitable for surgery.
- In the UK, Liquid Cartilage™ (ChondroFiller) is delivered at London Cartilage Clinic on Harley Street, led by Professor Paul Y. F. Lee. Visit londoncartilage.com to book an assessment.
Next steps
Where to go from here
These routes are selected from the topic and purpose of this article. They are guidance, not a diagnosis or treatment recommendation.
Learn more
Explore ChondroFiller
Read the reviewed ChondroFiller pathway, including who it may help and what happens next.
Self-assessment
Try the ChondroFiller suitability check
Answer a short set of questions for a useful, non-diagnostic next-step guide.
Talk to the team
Book a free discovery call
A non-medical call with the team to understand services and choose the right booking route.
Legal & Medical Disclaimer
This article is written by an independent contributor and reflects their own views and experience, not necessarily those of Liquid Cartilage. It is provided for general information and education only and does not constitute medical advice, diagnosis, or treatment.
Always seek personalised advice from a qualified healthcare professional before making decisions about your health. Liquid Cartilage accepts no responsibility for errors, omissions, third-party content, or any loss, damage, or injury arising from reliance on this material.
If you believe this article contains inaccurate or infringing content, please contact us at [email protected].