
ChondroFiller injection for focal wrist cartilage defects
Can wrist cartilage damage be treated without surgery?
For many patients, the first question after a wrist cartilage diagnosis is a simple one: does this mean an operation? For a specific group — those with a focal, well-defined cartilage defect rather than widespread joint damage — the answer is not necessarily.
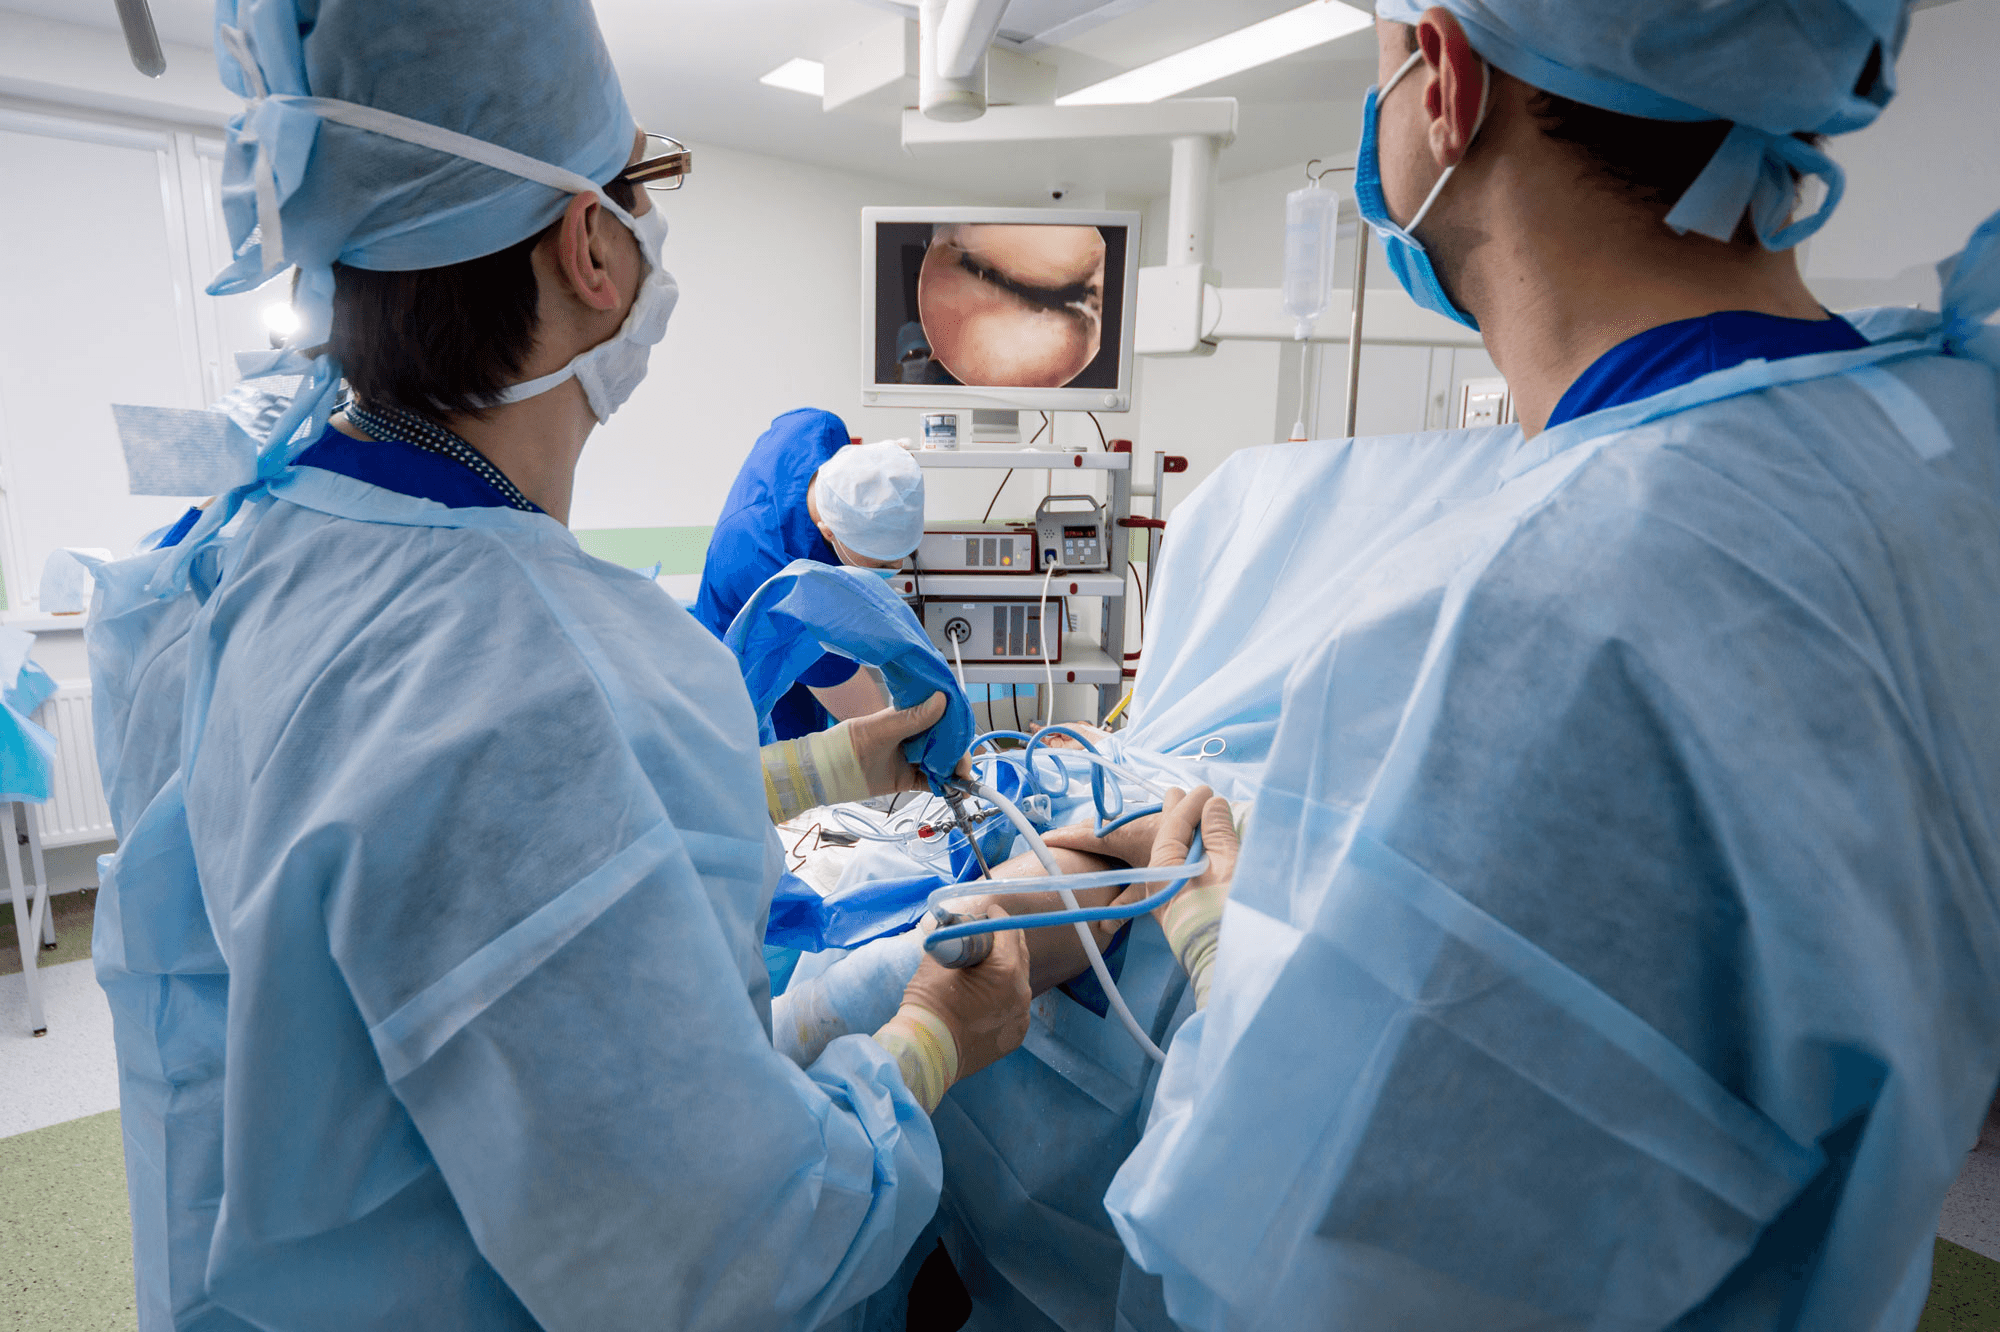
ChondroFiller injection is an ultrasound-guided outpatient procedure delivered at the London Cartilage Clinic on Harley Street. There is no theatre, no general anaesthetic, and no surgical incision. A cell-free collagen scaffold is placed directly into the defect under image guidance, where it sets in situ and creates a framework into which the body's own progenitor cells can migrate and begin building repair tissue.
What matters most at this stage is the word focal. ChondroFiller injection is designed for isolated, clearly defined cartilage damage — not for generalised wrist arthritis or diffuse cartilage wear across multiple surfaces. Patients with well-bounded defects and mechanically stable joints represent the realistic target group; those with advanced or widespread osteoarthritis are unlikely to be suitable.
The wrist has historically had fewer evidence-based cartilage repair options than the knee or hip, but that picture is beginning to change. Whether this pathway is appropriate for a given patient depends on defect size, location, and the broader condition of the joint — factors that can only be properly assessed at consultation.
What wrist cartilage damage looks like — and why it matters
Think of a cartilage defect as a pothole in an otherwise serviceable road surface. The pothole is discrete, bounded, and — in the right conditions — fillable. Generalised wrist osteoarthritis is more like a road worn thin over its entire length: the problem is diffuse, and patching one spot does not address the surface as a whole. The distinction is clinically decisive: scaffold repair is designed to fill the pothole, not resurface the road.
Distal radius fractures are one of the most common sources of focal wrist chondral defects. Bone heals; cartilage often does not. Research published in 2025 by Demmer et al. specifically examined residual chondral defects of 0.5–2 mm persisting after fracture fixation — confirming that this defect pattern is not incidental but a clinically recognised and studied entity that can persist long after the fracture itself has resolved.
Clinicians describe cartilage damage using Outerbridge or ICRS grading, both of which run from grade 1 (surface softening with the layer intact) through to grade 4 (full-thickness loss exposing bone). Scaffold repair is most meaningful at grades where structural fill can restore the joint surface rather than merely slow its deterioration.
Unlike bone, wrist cartilage does not regenerate spontaneously. Left unaddressed, focal defects tend to enlarge and deepen. A further prerequisite is mechanical stability: a ChondroFiller injection works best in a structurally stable wrist, so any underlying ligament or joint instability needs separate assessment before a scaffold pathway is considered.
How ChondroFiller injection works in the wrist
Unlike a pain-relief injection or a lubricating agent, ChondroFiller acts as a structural scaffold rather than a temporary symptom measure. Understanding how the material works explains both why it can be done without surgery and why precision of placement matters so much in a small joint like the wrist.
The hydrogel is delivered through a two-chamber syringe that combines its components at the point of injection. Once placed into the defect under ultrasound guidance, the material conforms to the cavity and sets within approximately 3–5 minutes, becoming a stable three-dimensional matrix anchored within the defect.
The next stage is where the biology takes over. The surrounding tissue contains mesenchymal progenitor cells — the body's own repair precursors — and the collagen scaffold creates a physical environment for them to migrate inward. A 2025 ex vivo study quantified this directly: ChondroFiller produced a 2.4-fold increase in DNA content within 14 days, confirming active cell recruitment rather than theoretical potential. Those cells then begin depositing collagen and glycosaminoglycans — the structural constituents of healthy cartilage.
In the wrist, where joint compartments are considerably smaller than the knee or hip, volume precision is non-negotiable. Typically only 0.2–0.3 mL of the 1 mL preparation is required, placed flush to the defect surface. Research published by Demmer et al. in 2025 found that fibrous tissue formation occurred exclusively in overfilled defects — making exact placement the single most critical technical variable in the wrist context.
Because the procedure is single-stage, there is no prior biopsy, no laboratory cell-culture interval, and no second operation — a meaningful practical contrast with two-stage cell-based approaches such as ACI or MACI.
What the clinical evidence shows
The Demmer et al. study, published in 2025, is the first clinical trial to examine ChondroFiller in the wrist specifically. The researchers applied the scaffold arthroscopically during fracture fixation — a theatre setting distinct from the ultrasound-guided outpatient injection pathway — but the cartilage quality data it generated speak directly to how the material performs in wrist tissue.
Among 25 patients whose residual chondral defects were filled with ChondroFiller, follow-up arthroscopy showed significantly better cartilage quality than in the untreated control group: median Outerbridge score 1.5 versus 3 (P=0.006) and median ICRS score 1 versus 3 (P=0.002). Both scales run from normal to full-thickness loss, so a lower number reflects structurally healthier cartilage — and the gap between the two groups was clinically as well as statistically meaningful.
Because this is the first study of its kind in the wrist, longer-term patient-reported outcomes and functional scores have not yet been published for this joint. What the Demmer findings establish is that the collagen scaffold supports meaningful cartilage repair in wrist tissue; whether that translates to durable pain relief over a three-to-five year horizon — as has been documented in the hip — remains to be confirmed.
For long-term durability, the hip currently provides the strongest anchor among comparable non-knee joints. In a cohort of 26 patients followed for 3–5 years (Mazek 2021), 81% maintained good or excellent results — consistent with the 70–85% meaningful-relief range reported across published knee, hip, and small-joint cohorts. Structural outcomes in these cohorts are captured by MOCART scoring, which measures how completely a defect has been filled with repair tissue on MRI; scores consistently in the 70–87 range indicate genuine structural integration rather than symptom palliation alone. The wrist-specific evidence points in the same direction; the longer-term data simply have not yet accumulated.
Who is a good candidate — and who is not
The clearest dividing line in candidacy is not the wrist joint itself but the nature of the damage. Isolated focal defects and diffuse joint degeneration call for entirely different pathways, and the ChondroFiller injection scaffold is designed only for the former.
An ideal candidate has a focal, well-defined chondral lesion — up to approximately 3 cm² — in a mechanically stable wrist with healthy surrounding cartilage borders. Post-traumatic damage fits this profile well: residual chondral defects following distal radius fractures represent a recognised clinical indication, because the surrounding joint typically remains structurally sound despite localised cartilage loss.
Where generalised OA changes the picture
When background joint degeneration is already established, the scaffold cannot function as designed. Evidence from the hip — the best-evidenced non-knee joint in the ChondroFiller literature — makes this concrete: in the Mazek 2021 cohort, patients with Tönnis grade 2–3 osteoarthritis consistently achieved poor results. The underlying reason is biological rather than arbitrary. In a diffusely degenerated joint, the progenitor-cell environment that ChondroFiller depends on for recruitment is compromised, and the local joint chemistry tends to suppress rather than support repair tissue formation. The same principle applies in the wrist — early- to mid-grade focal damage is the environment in which the scaffold performs.
The six-week protected window
A 2024 biomechanical in-vitro study confirmed that ChondroFiller under early cyclic loading (33 N) could not protect opposing cartilage surfaces — because the gel had not yet achieved stable mechanical integration. Approximately six weeks of protected, non-loaded activity is not an advisory precaution; it is the interval during which the scaffold sets within the defect and repair can begin. Shortening that window risks disrupting the material before it has done its job.
If there is one question worth bringing to a first consultation, it is this: is the cartilage damage discrete and contained, or has degeneration spread across the joint more broadly? That distinction — focal versus diffuse — is the practical starting point for determining whether this pathway is realistic.
Getting assessed at the London Cartilage Clinic
Liquid Cartilage™ / ChondroFiller injection is available in the UK at the London Cartilage Clinic on Harley Street — the UK's certified delivery centre for the product. Appointments can be booked directly at londoncartilage.com.
Professor Paul Y. F. Lee leads ChondroFiller delivery at the clinic. As with any technique-sensitive procedure, outcomes are influenced by how precisely the scaffold is placed — flush-level fill and accurate volume control are non-negotiable, as the clinical evidence makes clear.
Treatment is self-funded, starting from £3,000. The package includes consultation, ultrasound guidance, the product, IV antibiotic cover, and a six-week follow-up. Patients attending an initial assessment should bring any existing wrist imaging — MRI in particular helps the clinical team evaluate defect size, location, and the condition of the surrounding joint, and avoids unnecessary duplication.
The assessment is the appropriate point to discuss individual suitability, imaging requirements, and what recovery involves. A clinical opinion cannot be replaced by a checklist, and the consultation exists precisely to work through the detail.
- [1] Cartilage reconstruction using Chondrofiller in intra-articular distal radius fractures. (2025). https://doi.org/10.1186/s42836-025-00333-y https://doi.org/10.1186/s42836-025-00333-y
- [2] Development of an Ex Vivo Osteochondral Biomimetic Platform for Mechanistic Investigation of Cartilage Regeneration. (2025). https://doi.org/10.3390/ijms262311759 https://doi.org/10.3390/ijms262311759
- [3] Arthroscopic debridement with microfragmented adipose tissue for wrist and hand chondral lesions in professional athletes. (2026). https://doi.org/10.1016/j.hansur.2026.102636 https://doi.org/10.1016/j.hansur.2026.102636
Frequently Asked Questions
- ChondroFiller is a cell-free collagen scaffold injected under ultrasound guidance into cartilage defects. It sets within 3–5 minutes, creating a framework for the body's progenitor cells to migrate and build repair tissue.
- Ideal candidates have focal, well-defined chondral lesions up to approximately 3 cm² in a mechanically stable wrist with healthy surrounding cartilage. Post-traumatic damage from distal radius fractures represents a recognised indication.
- Treatment starts from £3,000. The package includes consultation, ultrasound guidance, the product, intravenous antibiotic cover, and a six-week follow-up.
- The 2025 Demmer study found significantly better cartilage quality in treated patients: median Outerbridge score 1.5 versus 3 in controls. Hip evidence shows 81% achieved good or excellent results over 3–5 years.
- A 2024 biomechanical study confirmed that early loading before six weeks risked disrupting the scaffold before stable mechanical integration. Six weeks is needed for setting and initial repair.
Next steps
Where to go from here
These routes are selected from the topic and purpose of this article. They are guidance, not a diagnosis or treatment recommendation.
Learn more
Explore ChondroFiller
Read the reviewed ChondroFiller pathway, including who it may help and what happens next.
Self-assessment
Try the ChondroFiller suitability check
Answer a short set of questions for a useful, non-diagnostic next-step guide.
Talk to the team
Book a free discovery call
A non-medical call with the team to understand services and choose the right booking route.
Legal & Medical Disclaimer
This article is written by an independent contributor and reflects their own views and experience, not necessarily those of Liquid Cartilage. It is provided for general information and education only and does not constitute medical advice, diagnosis, or treatment.
Always seek personalised advice from a qualified healthcare professional before making decisions about your health. Liquid Cartilage accepts no responsibility for errors, omissions, third-party content, or any loss, damage, or injury arising from reliance on this material.
If you believe this article contains inaccurate or infringing content, please contact us at [email protected].