
Can a ChondroFiller Injection Delay Knee Replacement?
The honest answer on delaying knee replacement
If your surgeon has mentioned knee replacement and you're wondering whether an injection could push that back, the short answer is: possibly — and for the right patient, the biological rationale is stronger than it might first appear.
For Grade II–III osteoarthritis, where meaningful joint space still remains, replacement is rarely an immediate necessity. The clinical question becomes whether ongoing cartilage loss can be slowed, or whether some structural recovery is achievable, before that threshold is crossed. ChondroFiller injection addresses that question differently from conventional pain-relief injections: rather than masking symptoms, the injectable collagen scaffold is designed to recruit the body's own stem cells and rebuild cartilage tissue in the defect itself — a meaningful distinction when the goal is preservation rather than palliation.
That said, no dedicated trial has yet measured time-to-total-knee-replacement as a primary endpoint for ChondroFiller specifically. The joint-preservation case rests on the regenerative biology of the scaffold, on published outcomes data, and on proxy evidence from comparable injection therapies — a well-grounded but still-evolving picture. The mechanism, the clinical data, and those proxy comparisons are covered in the sections that follow.
How the injectable scaffold works inside a deteriorating joint
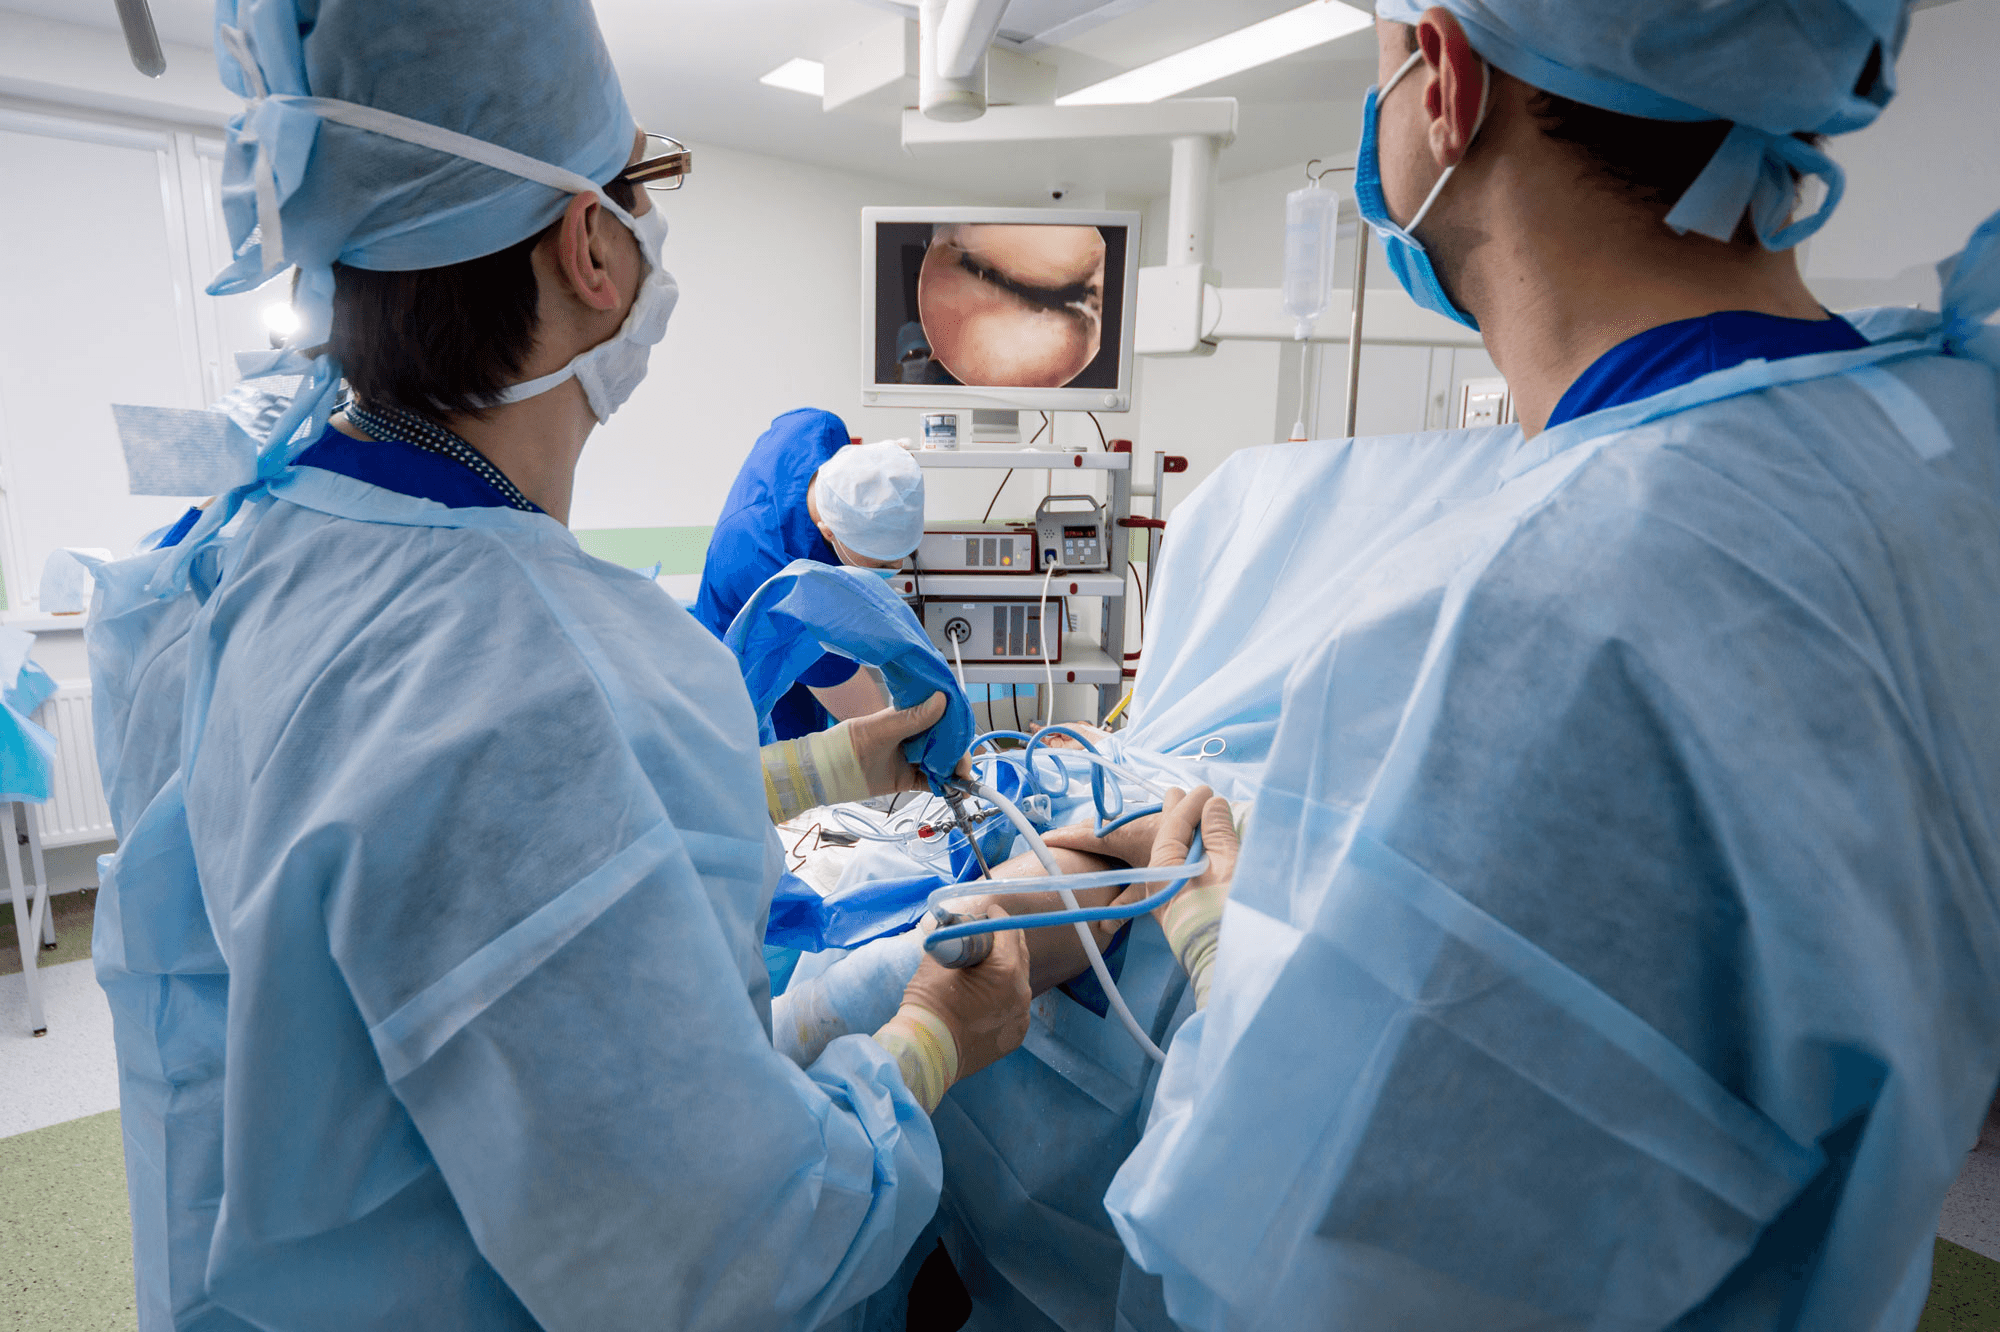
The scaffold itself is acellular — it contains no donor cells, no growth factors, and no biological material from another person. What it provides is a template: a matrix of Type I/III collagen that, once injected as a liquid under ultrasound guidance in an outpatient clinic, self-gels inside the defect and bonds to the cartilage surface.
The repair work is done entirely by the patient's own biology. The collagen matrix is chemotactic, meaning it draws mesenchymal stem cells from the surrounding tissue into the scaffold. Those cells migrate in, receive differentiation signals from the matrix environment, and begin producing native cartilage — type II collagen and proteoglycans — within the lesion. Over six to twelve months, new tissue fills the defect; the scaffold biodegrades and is resorbed, leaving nothing artificial behind in the joint.
This is why ChondroFiller injection occupies a different therapeutic category from viscosupplementation or corticosteroid injections. Those treatments act on the joint environment — modifying lubrication or dampening inflammation — without altering the cartilage surface itself. ChondroFiller injection targets the surface directly, using the defect as the site for tissue regeneration rather than symptom modulation.
For joint preservation, this distinction has practical weight. A deteriorating cartilage surface concentrates load on the subchondral bone and accelerates the breakdown cycle. Restoring some structural integrity to that surface — even partially — may slow that progression before the joint reaches a point where conservative options are exhausted.
What the clinical results show
Across more than 19,000 cases performed globally, published multi-centre data for ChondroFiller injection show consistent functional gains. In the knee, International Knee Documentation Committee (IKDC) scores improve by approximately 30 points — a shift that crosses the threshold for clinically meaningful benefit in most scoring frameworks. Hip patients see comparable gains on the Harris Hip Score (+33 points), and evidence extends meaningfully to ankle and smaller joints, reflecting the cross-joint application of the same scaffold mechanism.
MRI provides the structural confirmation. MOCART regeneration scores of 70–87 indicate that treated sites are filling with regenerated tissue rather than scar — a distinction that matters for long-term joint loading. The adverse event rate across this dataset is cited at approximately 0.06%, supporting the characterisation of this as a low-risk outpatient intervention.
The evidence is drawn from manufacturer-sponsored investigations and independent multi-centre literature; clinicians will weigh that mix of sources in the usual way, but the consistency of functional and imaging outcomes across sites lends the figures credibility. The dataset is strongest for focal cartilage defects, particularly Grade II–III lesions; less data exists for diffuse or end-stage disease. Crucially, time-to-surgery has not been a measured endpoint in any of these studies — which is where the broader injection literature becomes relevant.
What injection evidence tells us about delaying surgery
The benchmark comes from hyaluronic acid, the most studied intra-articular injection for knee OA. In a U.S. health claims analysis of 182,022 patients (Altman et al., 2015), HA users reached TKR at a median of 484 days after diagnosis, against 114 days in non-users. Patients completing five or more injection courses extended that to 3.6 years — a dose-dependent relationship across all groups (p<0.0001). A real-world ESCEO synthesis reached compatible conclusions: repeat intra-articular HA courses were associated with pain benefit lasting up to 40 months, roughly 50% lower analgesic use, and an estimated two-year delay in TKR need.
Polyacrylamide hydrogel (Arthrosamid) adds a second reference point. In a 24-month PROMs cohort of 314 knees, 15.6% of patients required TKR over two years — but that progression was concentrated in higher Kellgren–Lawrence grade cases. Lower OA grade independently predicted sustained functional benefit and avoidance of replacement, reinforcing the view that earlier intervention, when meaningful joint structure remains, carries the most preservation potential.
Neither product rebuilds cartilage. HA modifies joint lubrication; polyacrylamide hydrogel occupies synovial space. ChondroFiller injection targets the cartilage surface directly, recruiting the patient's own progenitor cells to lay down new tissue — addressing the structural reason the joint deteriorates rather than its symptoms alone. No dedicated time-to-TKR study for ChondroFiller exists yet, so exact equivalence with the HA or PAAG figures cannot be claimed. The biological rationale for scaffold-based delay is, however, at least as coherent as the mechanism that produced those results.
For patients who proceed, the maintenance schedule at the London Cartilage Clinic — bi-annual top-up injections combined with annual MRI monitoring and peptide supplementation — is designed to sustain cartilage integrity over time rather than treat isolated symptom flares. That iterative logic mirrors the repeat-course HA model that generated the strongest delay data in the published literature.
Patients most likely to benefit from this approach
Grade II–III osteoarthritis on Outerbridge or ICRS grading — where cartilage is eroded but meaningful joint space persists — represents the clinical sweet spot for ChondroFiller injection. The scaffold is validated for focal defects up to 3 cm², with extension to 6 cm² in appropriate cases. Patients with identifiable focal damage and residual cartilage remaining around the defect tend to derive the most sustained benefit; those with diffuse, bone-on-bone OA across multiple compartments are unlikely to be suitable.
Kellgren–Lawrence Grade III–IV cases are not automatically excluded, but they call for a different approach. A combined protocol — ChondroFiller injection to the cartilage surfaces alongside Arthrosamid hydrogel integrated into the synovial lining — treats the deteriorating joint at two anatomically distinct levels simultaneously. These are not interchangeable products: ChondroFiller is the regenerative scaffold recruiting new cartilage tissue; Arthrosamid is a hydrogel cushioning the joint environment. Each requires separate clinical justification.
The 24-month PAAG cohort data (N=314 knees) confirm what clinical judgment suggests: higher Kellgren–Lawrence grade independently predicts a greater chance of eventual TKR. Earlier intervention, when structure remains to preserve, consistently associates with better outcomes.
Age is less of a determining factor than disease stage. Mid-life patients with Grade II–III focal damage are the most common clinical profile, though the assessment at the London Cartilage Clinic carries no upper age limit. A consultation, not imaging alone, determines suitability.
Getting assessed at the London Cartilage Clinic
The evidence reviewed here does not prove that ChondroFiller injection delays knee replacement by a specific number of years — that trial has not yet been run. What it does support is a coherent biological case: a scaffold that recruits new cartilage tissue, placed in a joint still worth preserving, maintained through a structured monitoring programme, addresses the structural cause of deterioration rather than its symptoms alone. For Grade II–III patients who fit the profile described above, that distinction carries genuine weight.
If this sounds relevant, the practical next step is an assessment at the London Cartilage Clinic on Harley Street — the UK certified delivery centre for the ChondroFiller injection. A consultation reviews existing imaging, grades the defect, and determines whether a standalone injection or a combined protocol is appropriate. Professor Paul Y. F. Lee leads delivery of Liquid Cartilage™ in the UK, and technique precision in image-guided scaffold placement is a meaningful outcome variable. Book an assessment via londoncartilage.com.
- [1] Hyaluronic Acid Injections Are Associated with Delay of Total Knee Replacement Surgery in Patients with Knee Osteoarthritis: Evidence from a Large U.S. Health Claims Database. (2015). https://doi.org/10.1371/journal.pone.0145776 https://doi.org/10.1371/journal.pone.0145776
- [2] Polyacrylamide hydrogel injections in knee osteoarthritis: A PROMs-based 24-month cohort study. (2025). https://doi.org/10.1016/j.jcot.2025.103136 https://doi.org/10.1016/j.jcot.2025.103136
- [3] Efficacy and safety of hyaluronic acid in the management of osteoarthritis: Evidence from real-life setting trials and surveys. (2016). https://doi.org/10.1016/j.semarthrit.2015.11.008 https://doi.org/10.1016/j.semarthrit.2015.11.008
Frequently Asked Questions
- ChondroFiller uses a collagen scaffold to recruit the patient's own stem cells, which generate new cartilage tissue. Other injections like hyaluronic acid lubricate the joint without rebuilding cartilage.
- Published data show approximately 30-point improvements on the IKDC functional scoring scale. MRI imaging confirms treatment sites fill with regenerated tissue rather than scar, with MOCART scores of 70–87.
- Ideal candidates have Grade II–III osteoarthritis with focal cartilage defects and meaningful joint space remaining. Patients with diffuse, bone-on-bone disease across multiple compartments are unlikely to benefit.
- No dedicated trial has measured time-to-replacement for ChondroFiller specifically. Evidence from hyaluronic acid suggests delays ranging from 484 days to 3.6 years with repeat courses.
- The London Cartilage Clinic maintenance schedule recommends bi-annual top-up injections combined with annual MRI monitoring and peptide supplementation to sustain cartilage integrity over time.
Next steps
Where to go from here
These routes are selected from the topic and purpose of this article. They are guidance, not a diagnosis or treatment recommendation.
Learn more
Explore liquid cartilage treatment
Use a structured overview to narrow down the most useful next step for your situation.
Talk to the team
Book a free discovery call
A non-medical call with the team to understand services and choose the right booking route.
Legal & Medical Disclaimer
This article is written by an independent contributor and reflects their own views and experience, not necessarily those of Liquid Cartilage. It is provided for general information and education only and does not constitute medical advice, diagnosis, or treatment.
Always seek personalised advice from a qualified healthcare professional before making decisions about your health. Liquid Cartilage accepts no responsibility for errors, omissions, third-party content, or any loss, damage, or injury arising from reliance on this material.
If you believe this article contains inaccurate or infringing content, please contact us at [email protected].